Hormones and the Endocrine System
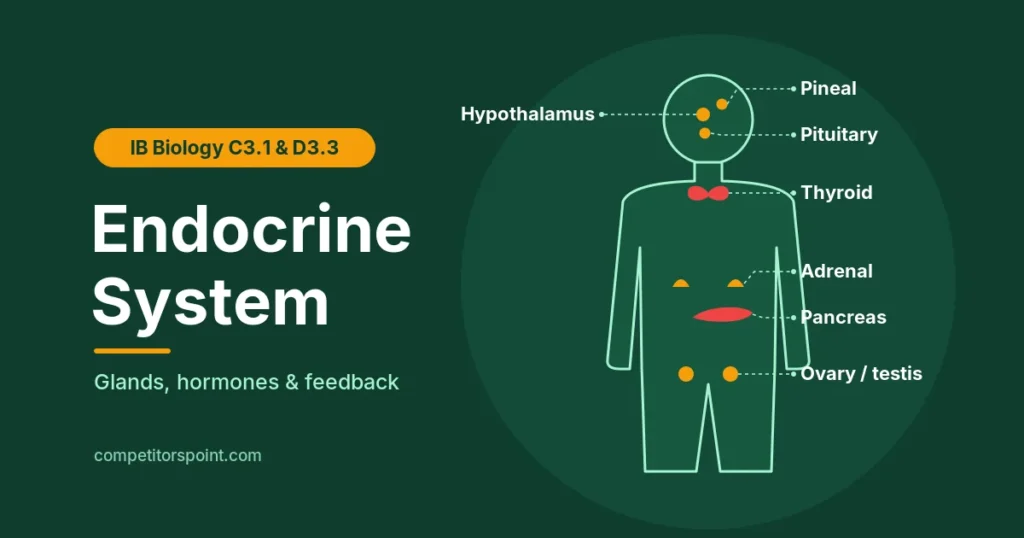
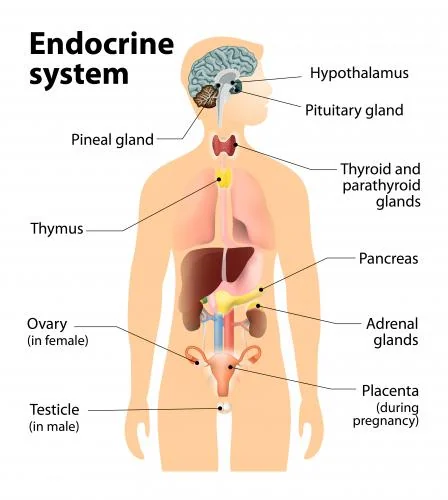
The endocrine system is the set of ductless glands and hormone-secreting tissues that release hormones directly into the blood. Hormones reach every part of the body but act only on target cells with matching receptors, regulating growth, metabolism, blood glucose, water balance and reproduction. Most are controlled by negative feedback, and the hypothalamus links the endocrine and nervous systems.
These endocrine system IB Biology notes cover hormones and endocrine glands, control by the hypothalamus and pituitary, adrenaline and vigorous activity, melatonin and sleep, blood glucose control by insulin and glucagon, type 1 and type 2 diabetes, thermoregulation with thyroxin, feedback, and how hormones act on target cells. Every section is mapped to the IB Biology guide (first assessment 2025), with HL content marked.
1 Endocrine glands and hormones
IB link: C3.1.3 (SL) integration of organs by hormonal and nervous signalling; C2.1.3 to C2.1.5 HL signalling chemicals and their effects.
The nervous system and the endocrine system jointly coordinate and regulate the physiological functions of the body. The neural system provides point-to-point, rapid coordination among organs, but it is short-lived. Nerve fibres do not reach every cell, and many cellular functions need continuous regulation. Hormones do that job. This page explains how the human endocrine system works for IB Biology, from the glands themselves to blood glucose, body temperature and cell signalling.
Practice MCQ
Which of the two systems of the body jointly coordinate and regulate the physiological functions in the body?
- a) The nervous system and the muscular system
- b) The nervous system and the endocrine system
- c) The respiratory system and the endocrine system
- d) The nervous system and the digestive system
Show answer
(b) Neural coordination is fast but short-lived and reaches only innervated cells; the endocrine system gives slower, longer-lasting, body-wide control.
Nervous system vs endocrine system
The nervous system and the endocrine system both carry messages between organs, but they do it in very different ways. IB C3.1.3 asks you to compare them and to see how they work together. For a plain-language overview, see the MedlinePlus guide to the endocrine system.
Swipe the table sideways to see every column.
| Feature | Nervous system | Endocrine system |
|---|---|---|
| Signal | Electrical impulse along a neuron, then a neurotransmitter across a synapse | Chemical (hormone) secreted into the blood |
| Route | Along nerve fibres to specific cells | In the blood to every cell; only cells with the right receptor respond |
| Speed | Very fast (milliseconds) | Slower (seconds to hours) |
| Duration of effect | Short; stops when impulses stop | Longer lasting (minutes to days) |
| Area affected | Localised: one muscle or gland | Often widespread: many tissues at once |
| Examples | Pain reflex, contraction of a skeletal muscle | Insulin lowering blood glucose, GH and growth, thyroxin and metabolic rate |
Glands of the endocrine system: endocrine vs exocrine
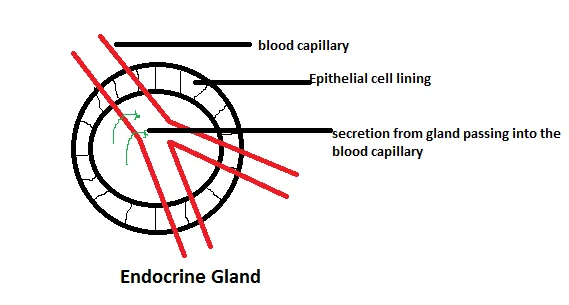
An exocrine gland has a duct. Its epithelial cells secrete into the duct, which carries the secretion to a body surface or into a cavity (e.g. salivary glands into the mouth, sweat glands onto the skin).
Endocrine glands are ductless. Their secretory epithelial cells release hormones into the surrounding tissue fluid, from where they enter the blood capillaries that run through the gland and travel to the rest of the body.
Practice MCQ
Which of the following statements is correct for endocrine glands?
- a) Endocrine glands are ductless glands
- b) Endocrine glands pour their secretions into ducts
- c) Both a and b
- d) Endocrine glands secrete digestive enzymes
Show answer
(a) Endocrine glands are ductless, so they secrete hormones directly into the blood capillaries.
What is a hormone? The messengers of the endocrine system
A hormone is a chemical messenger secreted by an endocrine gland into the blood, which carries it to distant target cells; it is effective in very small amounts. Hormones are not used as food, fuel or building material, but many can still be swallowed: thyroxine tablets, oral steroids and contraceptive pills all work when taken by mouth, whereas protein hormones such as insulin are digested in the gut and must be injected.
The word hormone comes from the Greek hormaein, “to excite or set in motion”. Many hormones are inhibitory, though; the name simply dates from when the first ones were discovered. Invertebrates have simple endocrine systems with few hormones, while vertebrates use a large number of chemicals as hormones.
Chemical nature of hormones
Hormones of the endocrine system belong to four chemical groups. The chemical group of a hormone decides whether it can cross the plasma membrane, and so how it acts (section 9). Peptide hormones are made on the rough ER, packaged by the Golgi apparatus into vesicles and released by exocytosis; steroid hormones are made from cholesterol.
Swipe the table sideways to see every column.
| Group | Examples | Soluble in | Receptor |
|---|---|---|---|
| Peptides, polypeptides and proteins | Insulin, glucagon, pituitary hormones, hypothalamic hormones | Water | On the plasma membrane |
| Steroids | Cortisol, aldosterone, testosterone, estradiol, progesterone | Lipid | Inside the cell (cytoplasm or nucleus) |
| Iodothyronines | Thyroid hormones (T3, T4) | Lipid | Inside the cell (nucleus) |
| Amino-acid derivatives (amines) | Adrenaline (epinephrine), noradrenaline, melatonin | Mostly water (catecholamines) | On the plasma membrane |
HL Signalling chemicals: local and distant effects
- Hormones, neurotransmitters, cytokines and calcium ions are all signalling chemicals in animals (C2.1.3).
- Hormones are chemically diverse: amines, proteins and steroids (C2.1.4).
- Hormones of the endocrine system have distant effects, carried in the blood; neurotransmitters have localised effects, diffusing only across a synaptic gap (C2.1.5).
2 Hypothalamus and pituitary gland
IB link: C3.1.13 (SL) control of the endocrine system by the hypothalamus and pituitary gland. Oxytocin links to D3.1.19 HL and ADH to D3.3.10 HL.
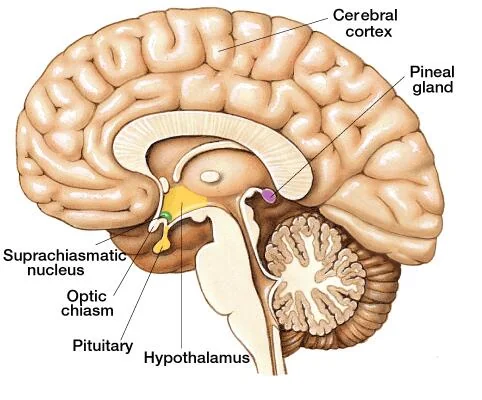
The hypothalamus links the nervous system to the endocrine system. It monitors the blood (temperature, osmotic concentration, hormone levels) and controls the pituitary gland, which in turn controls several other endocrine glands, so the pair sit at the top of the human endocrine system.
The hypothalamus
- A small region at the base of the brain, in the walls of the third ventricle, directly above the pituitary gland.
- It contains several groups of neurosecretory cells called nuclei: neurons that secrete hormones (neurohormones).
- Its hormones pass to the pituitary gland and regulate the synthesis and secretion of pituitary hormones.
- It is also part of the limbic system and controls the autonomic nervous system, body temperature, thirst and hunger.
- Some of its nuclei contain sensors that monitor the blood: body temperature, glucose concentration, osmotic concentration and the levels of several hormones. Others receive nerve impulses from the sense organs, so the hypothalamus can respond to changes both inside and outside the body.
Practice MCQ
Which of the following is true for the hypothalamus?
- a) It is the floor (basal part) of the diencephalon of the forebrain
- b) It contains groups of neurosecretory cells called nuclei
- c) Hormones secreted by the hypothalamus pass to the pituitary gland
- d) Hypothalamic hormones regulate the synthesis and secretion of pituitary hormones
- e) All of the above
Show answer
(e)
A stalk (the infundibulum) connects the hypothalamus to the pituitary gland, which sits in a bony cavity of the sphenoid bone called the sella turcica. The hypothalamus reaches the two lobes of the pituitary in two different ways:
- Anterior pituitary: neurosecretory cells release releasing and inhibiting hormones into a capillary bed in the hypothalamus. Blood from the superior hypophyseal arteries (branches of the internal carotid artery) carries them down the hypophyseal portal vein to a second capillary bed in the anterior pituitary.
- Posterior pituitary: the axons of some neurosecretory cells run down the stalk into the posterior pituitary (neurohypophysis) and release their hormones there, straight into the blood.
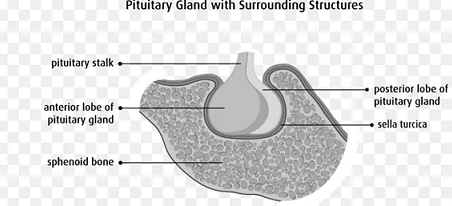
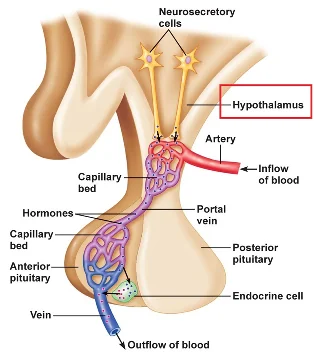
A portal vein is a vein that begins in one capillary bed and ends in a second capillary bed instead of going straight to the heart. The hypophyseal portal system lets hypothalamic hormones reach the anterior pituitary in high concentration, without being diluted in the general circulation.
Releasing hormones: how the hypothalamus controls the anterior pituitary
Neurosecretory cells of the hypothalamus secrete releasing hormones (and a few inhibiting hormones) into the portal vein. Each one makes the anterior pituitary release, or hold back, a particular hormone. Two examples you will meet again on this page are TRH, which triggers the release of TSH (thermoregulation, section 7), and GnRH, which triggers the release of FSH and LH at puberty and in the menstrual cycle. IB does not ask for a full list of releasing hormones.
Posterior pituitary hormones: made in the hypothalamus
Two hormones are made in the hypothalamus, carried down the axons and only stored and released by the posterior pituitary (neurohypophysis):
- Oxytocin, made mainly by the paraventricular nuclei: contracts the smooth muscle of the uterus during childbirth and causes milk ejection from the mammary glands. A synthetic form (Pitocin) is used to induce labour.
- Vasopressin (ADH, antidiuretic hormone), made mainly by the supraoptic nuclei: increases water reabsorption in the distal convoluted tubule and collecting duct of the kidney, so less, more concentrated urine is produced (see the HL box below).
Both nuclei make some of each hormone; “mainly” is the accurate word.
Practice MCQ
Which of the following hormones are released from the posterior pituitary?
- a) Oxytocin
- b) Vasopressin
- c) Both a and b
- d) ACTH
Show answer
(c) Both are made by neurosecretory cells of the hypothalamus; the posterior pituitary only stores and releases them. ACTH comes from the anterior pituitary.
HL Osmoregulation by ADH (D3.3.10)
- Osmoreceptors in the hypothalamus monitor the osmotic concentration of the blood (normally about 300 mOsm).
- If the blood becomes too concentrated (after sweating or drinking little), the hypothalamus makes the pituitary secrete more ADH.
- ADH binds receptors on cells of the collecting duct (and distal convoluted tubule). Vesicles carrying aquaporins, water channel proteins, fuse with the plasma membrane, so the membrane becomes much more permeable to water.
- Water is reabsorbed by osmosis into the salty medulla: a small volume of concentrated urine is produced and the blood is diluted back towards the set point.
- If the blood is too dilute, ADH secretion falls, aquaporins are taken back into vesicles inside the cells, little water is reabsorbed and a large volume of dilute urine is produced.
This is negative feedback: the response cancels the change that triggered it.
The pituitary gland: master gland of the endocrine system
- Also called the hypophysis; a small, pea-sized gland in the sella turcica.
- Called the master gland because its hormones control several other endocrine glands, though it is itself controlled by the hypothalamus.
- It secretes trophic (tropic) hormones, which stimulate other endocrine glands, and non-trophic hormones, which act directly on non-endocrine tissues.
SL How much detail do you need?
IB C3.1.13 asks for a general understanding of how the hypothalamus and pituitary control the endocrine system: the hypothalamus detects changes and controls the pituitary, which releases hormones that control other glands and organs. You are not required to know the differences between the mechanisms of the anterior and posterior pituitary, or the lists of releasing hormones.
Trophic hormones of the anterior pituitary
These act on other endocrine glands:
- TSH (thyroid-stimulating hormone, thyrotropin): stimulates the thyroid gland to secrete T3 and T4.
- FSH (follicle-stimulating hormone): in females, stimulates growth and development of ovarian follicles; in males, with androgens, regulates spermatogenesis.
- LH (luteinising hormone): in females, induces ovulation and maintains the corpus luteum; in males, stimulates the Leydig cells to secrete androgens.
- ACTH (adrenocorticotropic hormone): stimulates the adrenal cortex to secrete glucocorticoids.
🧠 Mnemonic: FLAT
FSH, LH, ACTH, TSH: the four trophic hormones of the anterior pituitary.
Non-trophic hormones of the anterior pituitary
These act directly on non-endocrine tissues:
- GH (growth hormone, somatotropin): increases protein synthesis and raises blood glucose. Much of its growth effect works through an intermediate: GH makes the liver release somatomedins, chiefly IGF-1 (insulin-like growth factor 1). IGF-1 is anabolic: it binds to cells of bone, cartilage, skeletal muscle and other tissues and promotes cell division and protein synthesis, so the body grows. GH also acts directly on fat cells, promoting lipolysis (fat breakdown), which supplies energy between meals and during fasting. GH is still secreted in adults, where it maintains and repairs tissues.
- Prolactin (PRL): stimulates the growth of the mammary glands and milk production. Prolactin levels rise steadily during pregnancy, but high progesterone and estrogen hold back milk secretion until after birth.
3 Thyroid and adrenal glands
IB link: C3.1.12 (SL) epinephrine (adrenaline) secretion by the adrenal glands; D3.3.5 (SL) thyroxin in thermoregulation.
The thyroid sets the metabolic rate and heat production of the body, and the adrenal medulla prepares the body for vigorous activity. Both are linked to the hypothalamus: the thyroid through TRH and TSH, the adrenal medulla through the nervous system.
Thyroid gland
- A butterfly-shaped gland in the neck.
- Two lobes lie on either side of the trachea, just below the larynx, joined by a thin flap of tissue called the isthmus.
- Each lobe is made of many follicles, the structural and functional units, richly supplied with blood vessels.
- Follicles are lined by cuboidal epithelium and filled with a gelatinous colloid (stored thyroglobulin).
- Follicular cells secrete T3 (triiodothyronine) and T4 (tetraiodothyronine or thyroxine), both made by iodination of the amino acid tyrosine.
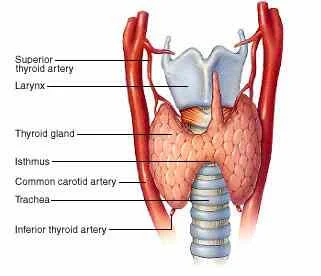
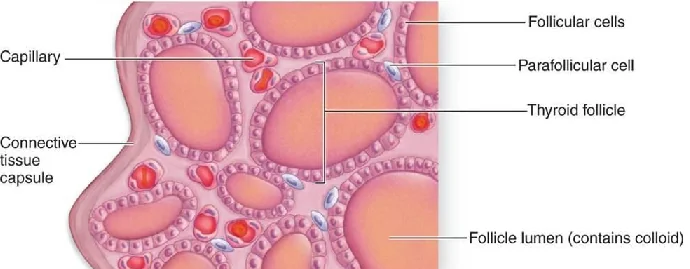
Secretion is controlled by the hypothalamus and pituitary: TRH (hypothalamus) → TSH (anterior pituitary) → T3 and T4 (thyroid). When T3 and T4 rise in the blood they feed back negatively on both the hypothalamus and the pituitary, reducing TRH and TSH (see the TRH–TSH feedback diagram in section 7).
Functions of T3 and T4
The thyroid releases much more T4 than T3, but T3 is the more active form: most T4 is converted to T3 in the tissues. Thyroid hormones act on almost every cell.
- Regulate the basal metabolic rate (BMR), the minimum energy use needed to stay alive. They increase cell respiration of carbohydrates, fats and amino acids, so energy and heat production rise.
- Increase protein synthesis; essential for normal physical and mental growth.
- Control the metabolism of carbohydrates, proteins and fats.
- All cells respond, but the most metabolically active tissues, the liver, skeletal muscle and brain, are the main targets. Each thyroxin molecule contains iodine atoms, so iodine is needed in the diet.
Beyond the syllabus Simple goitre: feedback without iodine
Simple goitre: enlargement of the thyroid caused by iodine deficiency in the diet. It is common in hilly regions where rain washes iodine out of the soil, so local crops contain little iodine. With too little iodine, little T3/T4 is made; negative feedback weakens, so TSH stays high and keeps stimulating the gland, which enlarges. Iodised salt prevents it.
Adrenal glands
- A pair of glands, one on top of each kidney; also called suprarenal glands.
- Two distinct regions: the central adrenal medulla and the outer adrenal cortex. They work as two separate endocrine glands.
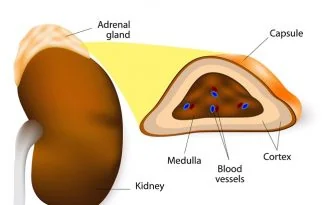
Adrenal medulla: adrenaline for vigorous activity
The adrenal medulla secretes adrenaline (epinephrine) and noradrenaline (norepinephrine), together called catecholamines; about 80% is adrenaline. They are secreted rapidly in response to stress and emergencies, so they are called the emergency hormones or hormones of fight or flight.
Adrenaline prepares the body for vigorous activity (IB C3.1.12):
Swipe the table sideways to see every column.
| Target | Effect of adrenaline | Why it helps vigorous activity |
|---|---|---|
| Heart | Faster heart rate and stronger contractions (more stroke volume) | Higher cardiac output delivers more O2 and glucose to muscles |
| Airways | Bronchioles dilate; breathing rate rises | More air reaches the alveoli, so more O2 in and CO2 out |
| Blood vessels | Arterioles to the gut, kidneys, skin and extremities constrict; arterioles to skeletal muscle and the liver (and the heart muscle) dilate | Blood is redirected to the organs doing the work |
| Liver and muscle | Glycogen broken down to glucose (glycogenolysis) | More glucose for respiration in the muscles |
| Adipose tissue | Lipolysis releases fatty acids | An extra fuel for respiration |
| Eyes, skin | Pupils dilate; sweating; hair stands up (piloerection) | Alertness; cooling during effort |
| Gut | Peristalsis and digestive secretions decrease | Energy and blood are saved for muscles |
Adrenaline binds adrenergic receptors in the plasma membrane of its target cells. Its secretion is controlled by the brain: it rises whenever vigorous activity may be needed, for example in response to a threat, or just before a race as an athlete prepares to start.
Noradrenaline’s main effect is vasoconstriction throughout the body, which raises blood pressure. The sympathetic nervous system releases noradrenaline from its nerve endings and works together with the adrenal medulla (the sympathetico-adrenal system), a clear example of the nervous system and endocrine system working together; the parasympathetic system has the opposite effects at rest.
The outer adrenal cortex secretes steroid hormones such as cortisol and aldosterone. The IB guide does not ask for them, so they are not covered in detail here.
4 Pineal gland, melatonin and the sex hormones
IB link: C3.1.11 (SL) modulation of sleep patterns by melatonin; D3.1.5 (SL) hormones of the menstrual cycle; D3.1.13, D3.1.17 and D3.1.19 HL puberty, pregnancy testing and childbirth; C2.1.13 HL oestradiol and progesterone.
The pineal gland ties the endocrine system to the day-night cycle, and the gonads secrete the sex hormones that IB uses in reproduction (D3.1).
Pineal gland and melatonin
- A pea-sized gland near the middle of the brain, attached to the roof of the third ventricle.
- Secretes melatonin, an amine hormone made from the amino acid tryptophan (through serotonin).
- Melatonin regulates the 24-hour (diurnal) rhythm of the body: the sleep-wake cycle and body temperature.
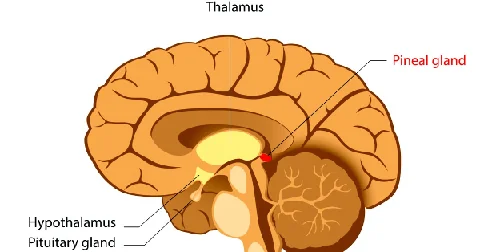
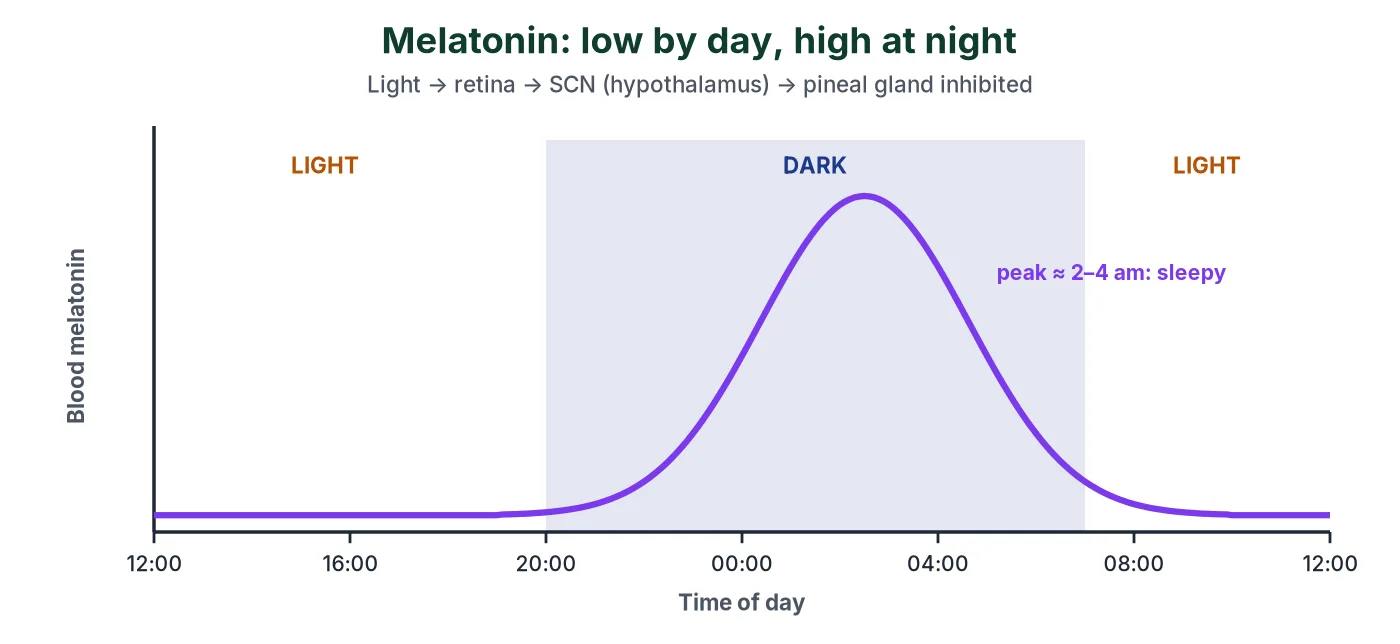
How melatonin sets the sleep cycle (IB C3.1.11): light falling on the retina sends nerve impulses to the suprachiasmatic nucleus (SCN) of the hypothalamus, the body’s master clock. From the SCN, a pathway through the spinal cord and sympathetic nerves reaches the pineal gland and inhibits melatonin secretion. So melatonin is low in daylight and we stay awake. As light fades in the evening the inhibition stops, melatonin rises, peaks in the middle of the night and makes us drowsy; it falls again towards morning.
SL More on the body clock (C3.1.11)
- The SCN keeps its own rhythm: SCN cells grown in culture, with no clues about the time of day, still follow a daily cycle.
- With no light cues at all, people still show a sleep-wake rhythm, but it runs slightly longer than 24 hours. Light at dusk and dawn resets the clock by a few minutes each day.
- The light signal comes from special ganglion cells in the retina that respond to blue light (wavelength about 460 to 480 nm) and send impulses to the SCN.
- Melatonin stays high for about 12 hours through the night, but only in dim light; even bright indoor lighting can stop its release.
- The liver removes melatonin from the blood quickly, so blood levels rise and fall closely with secretion.
- Melatonin also helps lower core body temperature at night.
- Babies do not develop a regular melatonin rhythm until about three months old, and children on average secrete more melatonin than adults.
SL Applications of melatonin
- Jet lag: after flying across time zones the SCN is out of step with local daylight. Light is the strongest signal for resetting the clock, so getting daylight (or avoiding bright light) at the right local times helps. Melatonin tablets are sometimes taken at local bedtime, but the evidence that they work is mixed, and the best dose and timing are not clear.
- Shift work and screen light at night suppress melatonin and disturb sleep.
Beyond the syllabus Melatonin and seasonal breeding
In animals that breed in a particular season, the length of the nightly melatonin pulse tells the body the time of year. In long-day breeders such as hamsters, long winter nights (more melatonin) switch the gonads off; in short-day breeders such as sheep, the longer melatonin signal of autumn switches breeding on.
Testes
- A pair of testes in the scrotum. They produce sperm and also secrete hormones.
- Leydig (interstitial) cells between the seminiferous tubules secrete androgens, mainly testosterone, an anabolic steroid.
- Beyond the syllabus Misuse of anabolic steroids (synthetic testosterone) causes acne and, through negative feedback that reduces LH and FSH, a fall in sperm count.
Practice MCQ
Leydig cells in the intertubular spaces produce androgens, mainly testosterone. Androgens are responsible for:
- a) Development, maturation and functions of the male accessory sex organs: epididymis, vas deferens, seminal vesicles, prostate gland and urethra
- b) Muscular growth, growth of facial and axillary hair, aggressiveness and low pitch of voice
- c) A major stimulatory role in spermatogenesis
- d) Anabolic (synthetic) effects on protein and carbohydrate metabolism
- e) All of the above
Show answer
(e)
Ovaries
- A pair of ovaries in the abdomen; they produce ova and hormones.
- Growing ovarian follicles secrete estrogen (mainly estradiol).
- After ovulation, the ruptured follicle becomes the corpus luteum, which secretes mainly progesterone.
Practice MCQ
The ovary produces estrogen and progesterone. Which of the following is a function of estrogen?
- a) It stimulates growth and activities of the female secondary sex organs
- b) It stimulates the development of growing ovarian follicles
- c) It causes the appearance of female secondary sex characters, such as a high-pitched voice, and mammary gland development
- d) It regulates female sexual behaviour
- e) All of the above
Show answer
(e)
Practice MCQ
Which of the following is a function of progesterone?
- a) It supports pregnancy
- b) It acts on the mammary glands and stimulates the formation of alveoli
- c) It stimulates milk secretion after birth
- d) Both a and b
Show answer
(d) Progesterone maintains the uterus lining in pregnancy and prepares the alveoli of the mammary glands. Milk secretion is driven by prolactin; the high progesterone level in pregnancy actually holds milk production back until after birth, when progesterone falls.
Reproductive hormones in the IB guide
Swipe the table sideways to see every column.
| Statement | Hormones | Key idea |
|---|---|---|
| D3.1.5 (SL) | FSH, LH, oestradiol, progesterone | Control the ovarian and uterine cycles by negative and positive feedback (LH surge) |
| D3.1.7 (SL) | Hormone drugs | IVF: normal secretion is suppressed, then high doses of FSH cause superovulation |
| D3.1.13 HL | GnRH, LH, FSH, sex steroids | Rising GnRH from the hypothalamus starts puberty |
| D3.1.17 HL | hCG | Pregnancy tests detect hCG with monoclonal antibodies |
| D3.1.19 HL | Progesterone, oxytocin | Progesterone maintains pregnancy; falling progesterone and positive feedback on oxytocin drive childbirth |
5 Pancreas and regulation of blood glucose
IB link: D3.3.1 (SL) homeostasis; D3.3.2 (SL) negative feedback loops; D3.3.3 (SL) regulation of blood glucose by insulin and glucagon.
Blood glucose is a homeostatic variable: it is kept close to a set point of about 5 mmol L−1 (90 mg dL−1) despite meals, fasting and exercise, normally staying between about 4 and 8 mmol L−1. The whole blood volume holds only about 5 g of glucose, so eating or exercise can change the concentration quickly. Too high damages blood vessels and nerves; too low starves the brain. The pancreas controls it by negative feedback, the best-known example of the endocrine system in homeostasis.
SL What homeostasis means (D3.3.1, D3.3.2)
- Homeostasis is keeping the internal environment within preset limits, despite changes outside the body.
- IB names four homeostatic variables in humans: body temperature, blood pH, blood glucose concentration and blood osmotic concentration.
- Each is controlled by negative feedback, which returns the variable to its set point whether it has risen above it or fallen below it.
The pancreas: a mixed gland
- The pancreas is both exocrine (pancreatic juice with enzymes, into the duodenum) and endocrine.
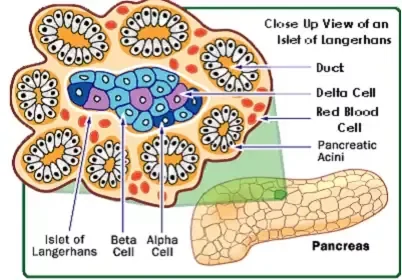
- The endocrine part is the islets of Langerhans: about 1 to 2 million clusters of cells, only 1 to 2% of the pancreatic tissue.
- α (alpha) cells secrete glucagon; β (beta) cells secrete insulin.
- Beyond the syllabus δ (delta) cells secrete somatostatin, which inhibits the release of both insulin and glucagon; PP cells secrete pancreatic polypeptide, which inhibits the secretion of pancreatic (exocrine) juice.
The blood glucose control loop
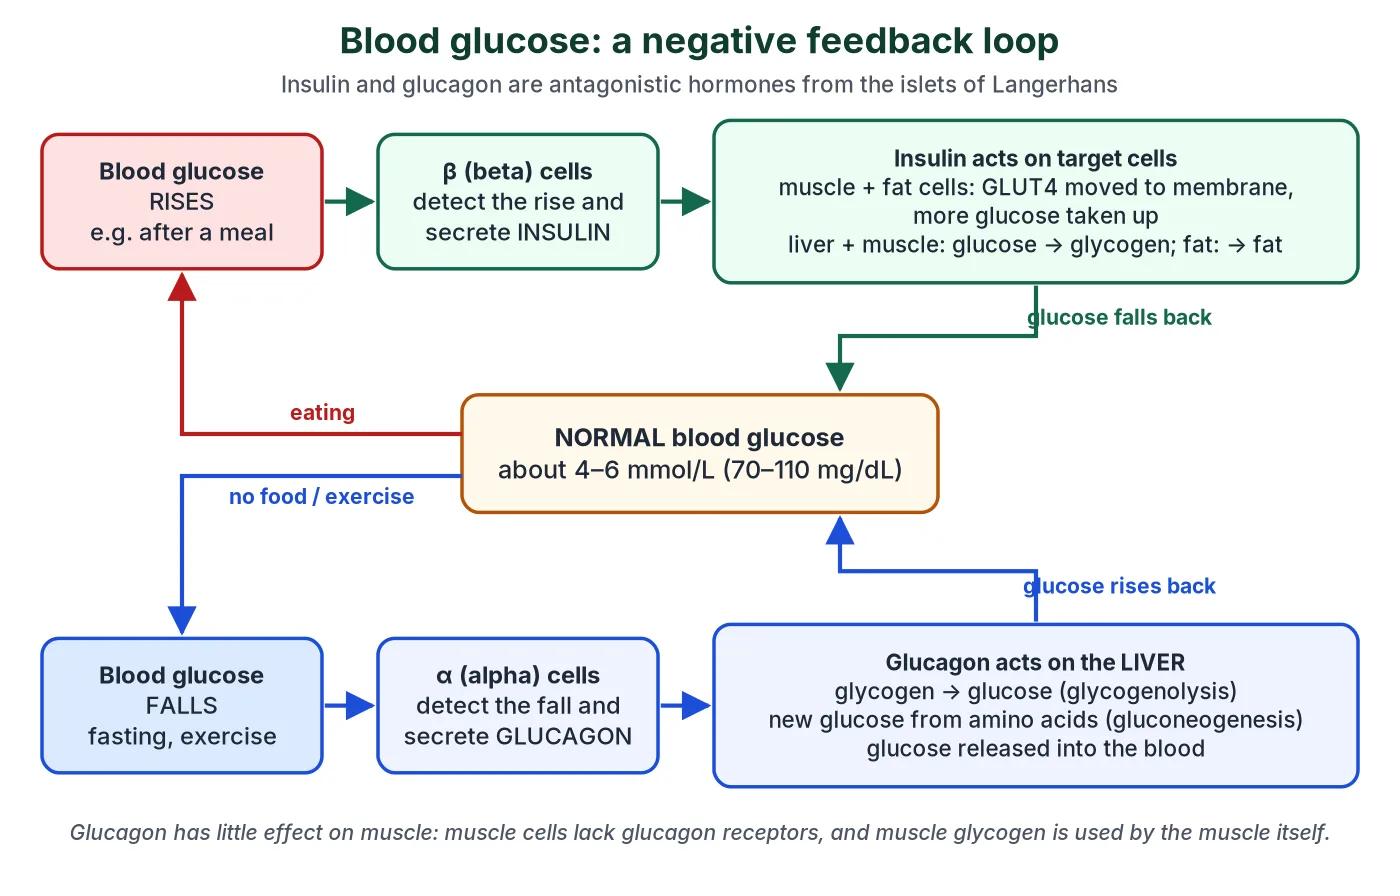
- The islet cells themselves are the receptors: they detect the glucose concentration of the blood flowing through the pancreas.
- If glucose rises, β cells secrete insulin into the blood. Its targets are liver cells, skeletal muscle cells and adipose (fat) cells, which take up glucose and store it as glycogen or fat.
- If glucose falls, α cells secrete glucagon. Its main target is the liver, which breaks down glycogen and makes new glucose, then releases glucose into the blood.
- In each case the response cancels the change: negative feedback returns blood glucose to the set point.
- Insulin and glucagon are antagonistic hormones: they have opposite effects on the same variable.
Insulin does not last long in the blood: like most hormones it is broken down by the cells it acts on. So the β cells keep secreting it for as long as blood glucose stays high, starting within minutes of a meal and often continuing for several hours.
Try it: what happens to blood glucose…
After a meal Blood glucose rising
Glucose absorbed from the gut raises blood glucose. β cells detect the rise and secrete insulin; α cells secrete less glucagon. Muscle and fat cells move GLUT4 transporters into their membranes and take up glucose; liver and muscle convert it to glycogen (glycogenesis); fat cells convert it to fat. Blood glucose falls back to normal.
Overnight fast Blood glucose falling
Between meals and overnight, glucose is used up and blood glucose starts to fall. α cells detect the fall and secrete glucagon; insulin falls. Glucagon acts on liver cells: glycogen is broken down to glucose (glycogenolysis) and new glucose is made from amino acids and glycerol (gluconeogenesis). The liver releases glucose and blood glucose rises back to normal.
A sprint or an exam Stress or vigorous activity
Muscles take up glucose fast. Adrenaline from the adrenal medulla, with glucagon, triggers glycogenolysis in the liver and in the muscles themselves, while insulin secretion is held down. In longer stress, cortisol adds gluconeogenesis. Blood glucose is kept up so the muscles and brain never run short.
Don’t mix these up
- Glucose: the sugar in the blood. Glycogen: the storage polysaccharide in liver and muscle. Glucagon: the hormone that makes the liver break glycogen down.
- Gluconeogenesis = making new glucose; glycogenolysis = splitting glycogen; glycogenesis = making glycogen.
- Glucagon acts mainly on the liver; muscle cells have no glucagon receptors and keep their glycogen for their own use.
6 Insulin and glucagon
IB link: D3.3.3 (SL) control of insulin and glucagon secretion, transport in the blood and effects on target cells; C2.1.10 and C2.1.11 HL adrenaline and insulin receptors.
Insulin and glucagon are the two endocrine system hormones that matter most for blood glucose. Both are peptide hormones from the islets of Langerhans, carried in the blood plasma to their target cells.
Swipe the table sideways to see every column.
| Insulin | Glucagon | |
|---|---|---|
| Secreted by | β cells | α cells |
| Chemical nature | Peptide hormone of 51 amino acids in two chains | Peptide hormone (29 amino acids) |
| Secreted when | Blood glucose is high (hyperglycaemia) | Blood glucose is low (hypoglycaemia) |
| Main targets | Liver, skeletal muscle, adipose tissue | Liver (hepatocytes) |
| Effects | Increases glucose uptake and use by cells (for example in glycolysis) (GLUT4 in muscle and fat); glucose → glycogen (glycogenesis) in liver and muscle; glucose → fat in adipocytes; increases amino acid uptake and protein synthesis | Glycogen → glucose (glycogenolysis) in the liver; gluconeogenesis; the liver releases this glucose into the blood (muscle has no glucagon receptors, so it is not a target) |
| Effect on blood glucose | Lowers it: hypoglycaemic hormone | Raises it: hyperglycaemic hormone |
HL Cell signalling: how insulin and adrenaline act
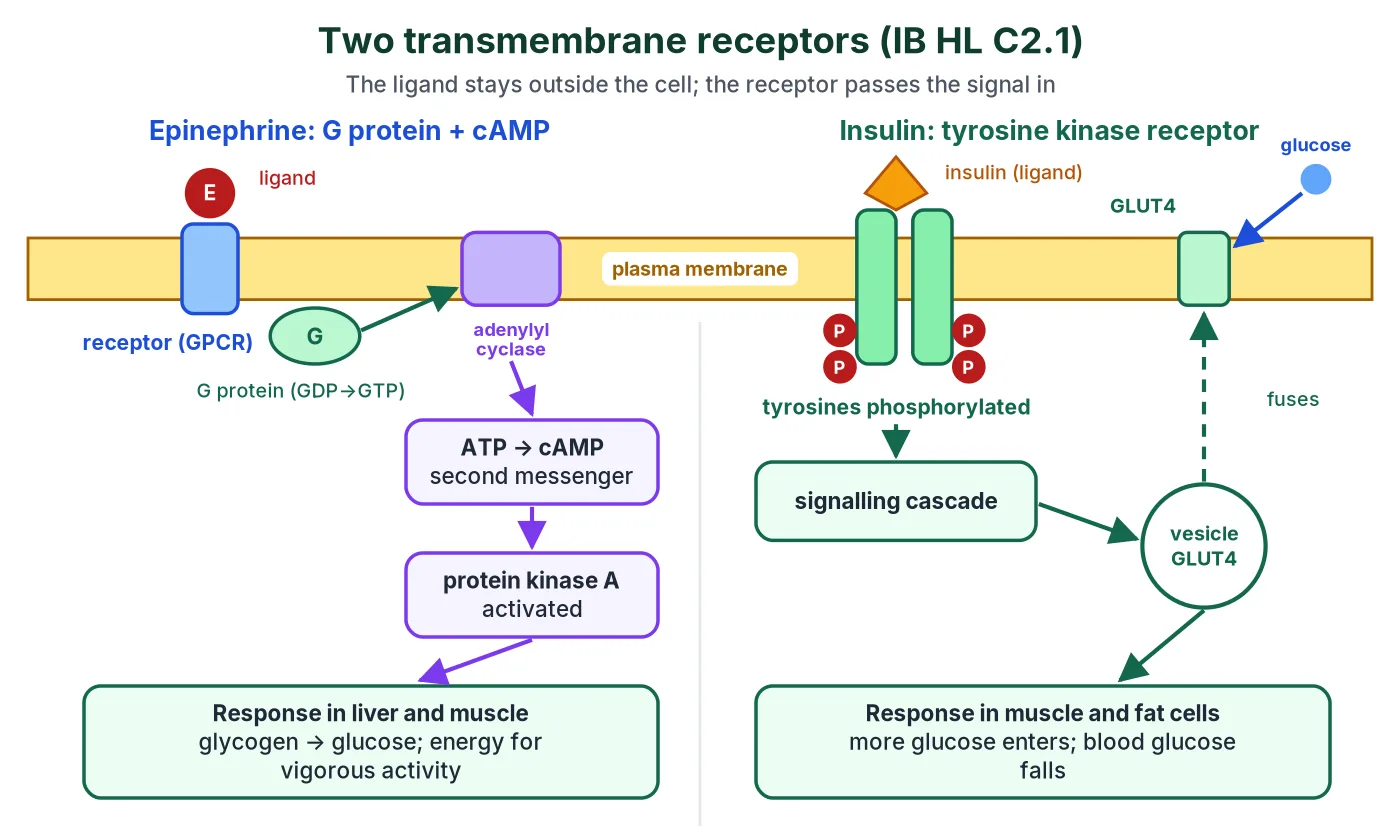
In the endocrine system, a signalling chemical is called a ligand; its receptor is a protein with a binding site specific to that ligand. Binding starts a signal transduction pathway inside the cell.
- Transmembrane receptors span the plasma membrane: their outside has hydrophilic amino acids and the part crossing the membrane has hydrophobic ones. They bind hydrophilic ligands (peptides, adrenaline) that cannot enter the cell.
- Intracellular receptors in the cytoplasm or nucleus bind hydrophobic ligands (steroids) that diffuse through the membrane (section 9).
- Adrenaline binds a G protein-coupled receptor. The activated G protein switches on adenylyl cyclase, which makes cyclic AMP (cAMP), the second messenger; cAMP activates protein kinase A, leading, in liver and muscle, to glycogen breakdown.
- Insulin binds a receptor with tyrosine kinase activity. Tyrosines on the inside of the receptor become phosphorylated, a chain of reactions follows, and vesicles carrying GLUT4 glucose transporters move to and fuse with the plasma membrane, so more glucose enters the cell.
7 Hormonal control of metabolism and body temperature
IB link: D3.3.5 (SL) thermoregulation as an example of negative feedback; D3.3.6 (SL) thermoregulation mechanisms in humans. The growth table is background reading.
The endocrine system controls growth and metabolism through several hormones acting together. GH and thyroxine are the main growth hormones; insulin, glucagon, adrenaline and cortisol decide whether fuel is stored or used.
Swipe the table sideways to see every column.
| Hormone | Source | Effect on growth and metabolism |
|---|---|---|
| Growth hormone (GH) | Anterior pituitary | Growth of bones and muscles through IGF-1 from the liver; protein synthesis; lipolysis; raises blood glucose |
| Thyroxine (T4) and T3 | Thyroid | Sets the basal metabolic rate and heat production; needed for growth and brain development |
| Insulin | Pancreas β cells | Anabolic: glucose uptake and storage, fat synthesis, protein synthesis |
| Glucagon, adrenaline | Pancreas α cells, adrenal medulla | Mobilise stored fuel: glycogenolysis, lipolysis |
| Cortisol | Adrenal cortex | Gluconeogenesis, glucose sparing, protein breakdown during long-term stress |
| Testosterone, estrogen | Testes, ovaries | Growth spurt and secondary sexual characters at puberty; testosterone is anabolic (muscle) |
Thyroxine, metabolic rate and body temperature
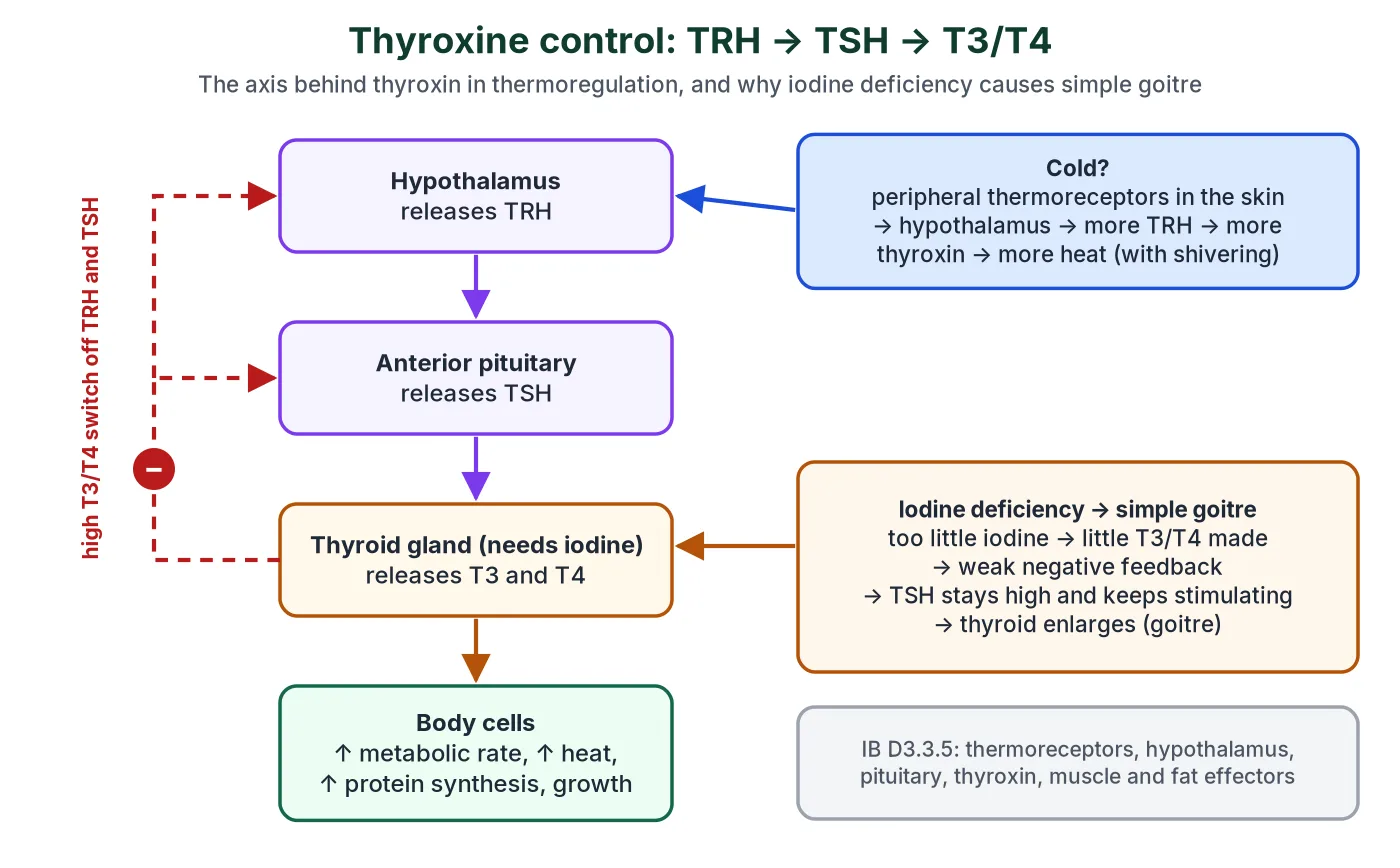
Body temperature is another homeostatic variable controlled by negative feedback (IB D3.3.5); here the nervous system and the endocrine system act together. Peripheral thermoreceptors in the skin and receptors in the hypothalamus detect temperature changes. When the body is cold, the hypothalamus increases TRH, the pituitary releases more TSH and the thyroid releases more thyroxin. Thyroxin raises the metabolic rate of cells, so more heat is released by respiration. Other effectors work at the same time:
Swipe the table sideways to see every column.
| When the body is too cold | When the body is too hot |
|---|---|
| Vasoconstriction of skin arterioles: less heat lost | Vasodilation of skin arterioles: more heat lost |
| Shivering: skeletal muscles contract rapidly, releasing heat | Sweating: evaporation of sweat cools the skin |
| Uncoupled respiration in brown adipose tissue: energy released as heat instead of ATP | Less thyroxin; lower metabolic rate |
| Hair erection (piloerection): traps a layer of air | Hairs lie flat |
SL Thermoregulation details IB expects (D3.3.5, D3.3.6)
- The human set point for core temperature is close to 37 °C. During an infection the set point is raised (fever), which helps the immune system remove pathogens.
- Peripheral thermoreceptors in the skin detect the outside conditions early; central thermoreceptors in the body core, including the hypothalamus, detect the core temperature. The hypothalamus is the integrating centre.
- The hormone chain: the hypothalamus secretes TRH (a tripeptide) → the pituitary secretes TSH (a glycoprotein) → the thyroid secretes thyroxin, which raises the metabolic rate of cells, especially in the liver, muscle and brain.
- Effector tissues: skeletal muscle makes heat when it contracts (shivering); subcutaneous fat insulates; brown adipose tissue makes heat quickly, which matters most in newborn babies and small mammals.
- Birds and mammals also use behaviour, such as seeking shade or sun, or changing clothing, but IB only asks for the physiological details in humans.
For how the hypothalamus works with the rest of the nervous system, see Integration of Body Systems.
8 Hormonal feedback mechanisms
IB link: D3.3.2 (SL) negative feedback loops; D3.1.5 (SL) positive and negative feedback in the menstrual cycle; C2.1.14 HL regulation of cell signalling pathways by feedback.
Feedback is how the endocrine system controls itself. Most hormone secretion is controlled by feedback: the result of a hormone’s action changes how much of the hormone is secreted.
Negative feedback in the endocrine system
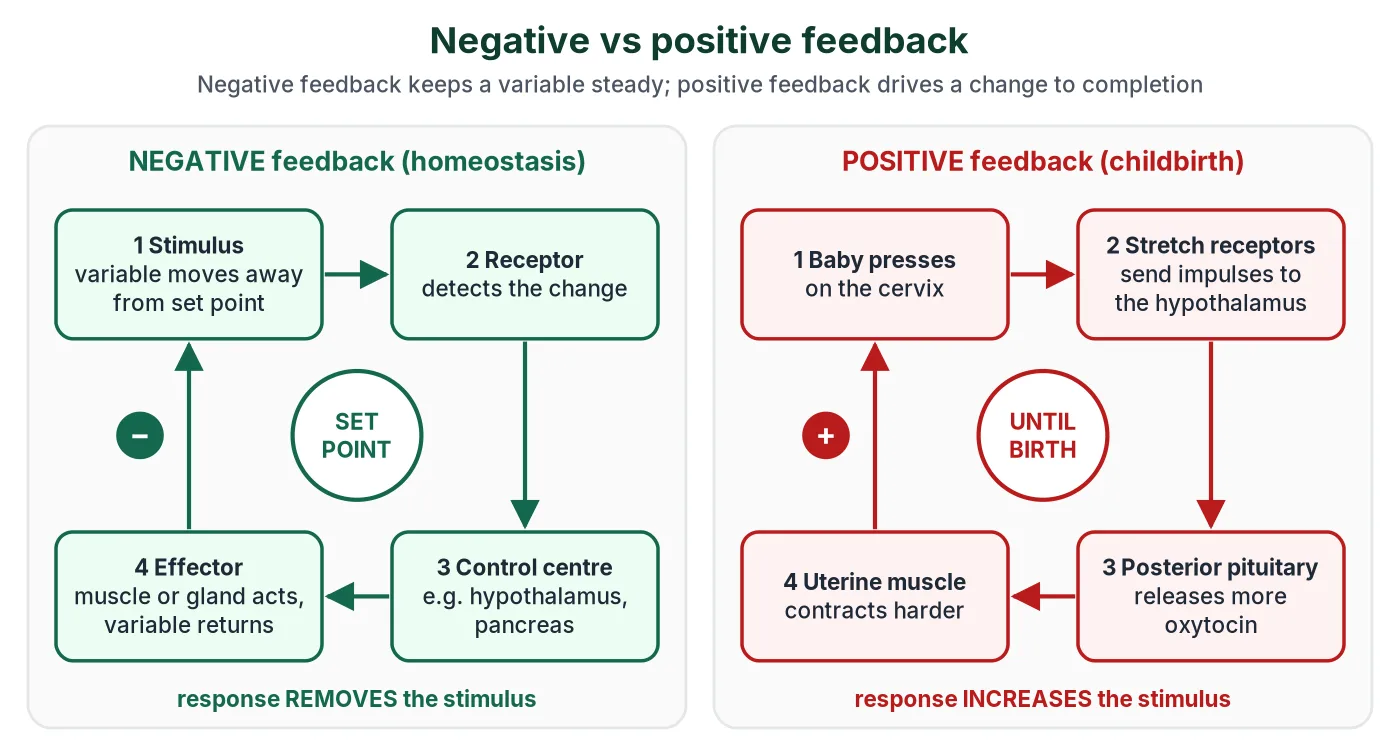
In negative feedback the response reverses the change that caused it. If a variable rises above its set point, the response lowers it; if it falls below, the response raises it. This keeps homeostatic variables within narrow limits.
Swipe the table sideways to see every column.
| Variable | Detected by | Hormone response | Result |
|---|---|---|---|
| Blood glucose | α and β cells of islets | High: insulin. Low: glucagon | Glucose back to about 5 mmol L−1 |
| Thyroxine level | Hypothalamus and anterior pituitary | High T3/T4 reduce TRH and TSH | Thyroxine stays steady |
| Blood osmotic concentration | Osmoreceptors in hypothalamus | High: more ADH. Low: less ADH | Water reabsorption adjusted |
| Body temperature | Thermoreceptors, hypothalamus | Cold: more TSH and thyroxin | Heat production rises |
Many hypothalamus-pituitary axes work by long-loop negative feedback: the final hormone (thyroxine, cortisol, testosterone, estradiol) inhibits both the hypothalamus and the anterior pituitary. This is the commonest control pattern in the human endocrine system.
Positive feedback
In positive feedback the response increases the change, so it grows until some outside event ends it. The endocrine system uses it for changes that need to be completed quickly, not for homeostasis.
- Childbirth: stretching of the cervix → more oxytocin → stronger uterine contractions → more stretching, until the baby is born.
- The LH surge: before ovulation, high oestradiol switches from negative to positive feedback on the hypothalamus and pituitary, causing a surge of LH that triggers ovulation.
- Milk ejection: suckling → oxytocin → milk let-down → more suckling.
Why homeostasis uses negative feedback
- Negative feedback returns a variable to the set point from values above or below it, so the internal environment stays stable.
- Positive feedback would push a variable further from its set point, so it is only safe for one-off events that end on their own.
Antagonistic and synergistic hormones
Hormones of the endocrine system often act in pairs or teams.
- Antagonistic hormones have opposite effects on the same variable: insulin and glucagon (blood glucose).
- Synergistic hormones work together to produce a bigger combined effect: estrogen, progesterone, prolactin and oxytocin together prepare the mammary glands and produce and eject milk; glucagon, adrenaline and cortisol together raise blood glucose.
Beyond the syllabus Nervous and hormonal antagonism at the heart
Heart rate is raised by adrenaline and noradrenaline (through β-receptors, a G protein and more cAMP) and lowered by acetylcholine from the vagus nerve. Acetylcholine acts through muscarinic receptors linked to an inhibitory G protein: cAMP falls and K+ channels open. Acetylcholine is a neurotransmitter here, not a hormone.
9 Mechanism of hormone action HL
IB link: C2.1.6 to C2.1.13 HL receptors and signal transduction. SL students only need the idea that hormones act on target cells with matching receptors.
Hormones of the endocrine system travel in the blood to every cell, but only target cells respond, because only they have receptors for that hormone. A hormone binding to its receptor forms a hormone-receptor complex, and each receptor is specific to one hormone. The hormone is the first messenger.
- Membrane-bound receptors are on the plasma membrane of target cells. They bind water-soluble hormones (peptides, proteins, catecholamines), which cannot cross the lipid bilayer.
- Intracellular receptors are inside the cell, mostly in the nucleus (nuclear receptors). They bind lipid-soluble hormones: steroids (corticoids, testosterone, estrogen, progesterone) and iodothyronines (T3, T4), which diffuse through the membrane.
Lipid-soluble hormones: steroids and thyroid hormones
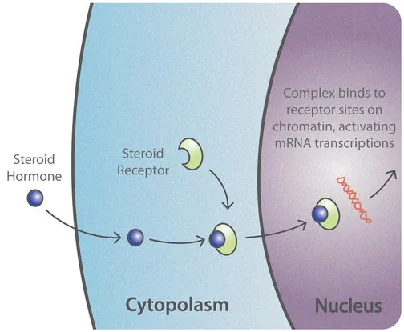
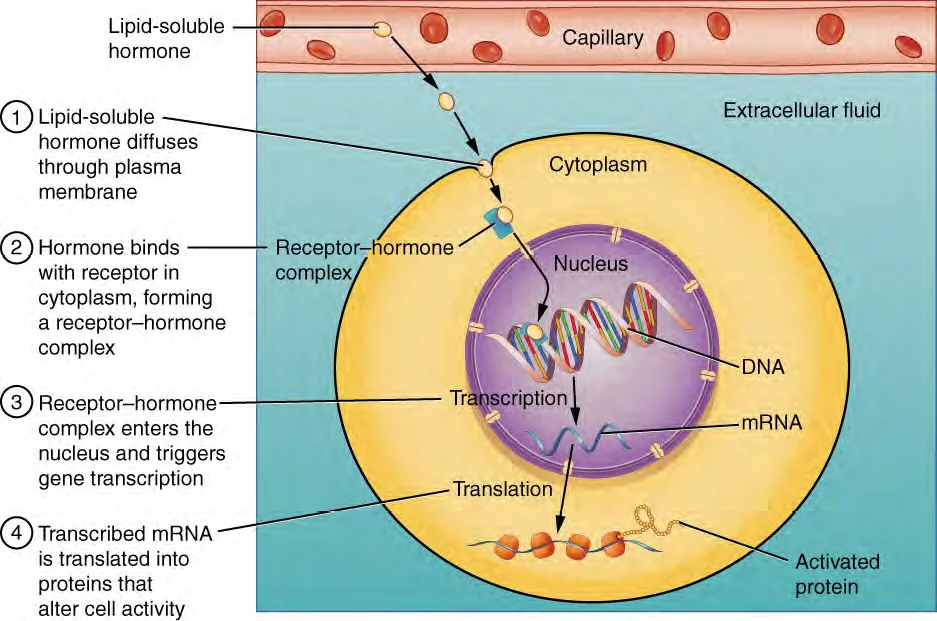
- The hormone diffuses through the plasma membrane into the target cell.
- It binds a receptor protein in the cytoplasm or nucleus to form a hormone-receptor complex.
- The complex binds a specific DNA sequence in the nucleus.
- Transcription of particular genes is switched on (or off), making mRNA.
- The mRNA is translated into new proteins, such as enzymes or membrane channels, which change the cell’s activity.
Because they work through gene expression, these hormones act more slowly but their effects last longer, which is typical of the endocrine system.
Water-soluble hormones: second messengers
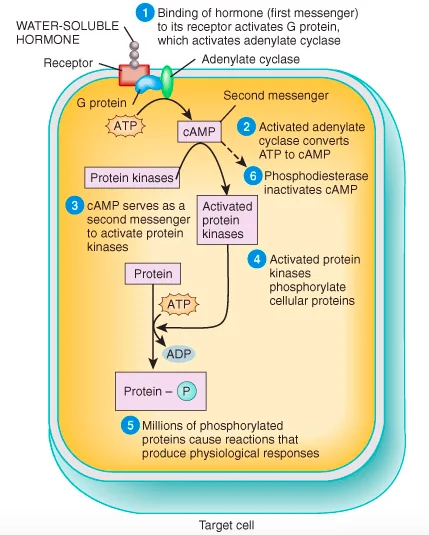
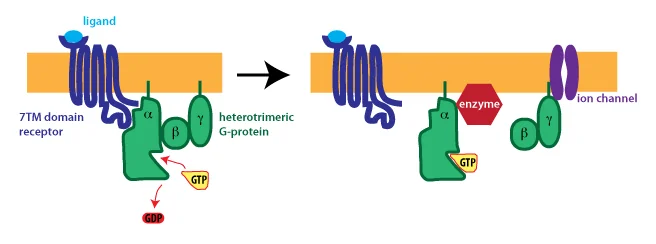
These hormones do not enter the cell. The receptor passes the signal inside:
- The hormone binds its membrane receptor.
- The receptor activates a G protein on the inside of the membrane; the G protein has α, β and γ subunits, and the α subunit swaps its GDP for GTP.
- The activated G protein activates the enzyme adenylate cyclase.
- Adenylate cyclase converts ATP into cyclic AMP (cAMP) + pyrophosphate (PPi).
- cAMP is the second messenger. It activates protein kinase, which was present in an inactive form.
- The protein kinase phosphorylates other enzymes, setting off the reactions that make up the cell’s response. One hormone molecule can lead to millions of product molecules (amplification).
- Common second messengers: cAMP, cGMP, IP3 (inositol trisphosphate), DAG (diacylglycerol) and Ca2+. IP3 and DAG are made by splitting the membrane lipid PIP2, which is their precursor, not a messenger itself.
- Insulin is different: its receptor is itself an enzyme (a receptor tyrosine kinase), not a G protein-coupled receptor (see the HL box in section 6).
HL Steroid hormones and their target cells
- Oestradiol, progesterone and testosterone bind intracellular receptors; the activated receptor binds specific DNA sequences and promotes transcription (C2.1.12).
- Oestradiol acts on cells in the hypothalamus that secrete GnRH; progesterone acts on cells of the endometrium, keeping it ready for implantation (C2.1.13).
10 Diabetes mellitus: type 1 and type 2
IB link: D3.3.4 (SL) physiological changes behind type 1 and type 2 diabetes, with risk factors, prevention and treatment.
Diabetes mellitus is the endocrine disorder IB asks about. You need the physiological changes behind type 1 and type 2, their risk factors, and how each is prevented and treated. For more on hormone disorders in general, see the MedlinePlus overview of endocrine diseases.
Diabetes mellitus: the commonest endocrine system disorder
Diabetes mellitus is prolonged hyperglycaemia caused by too little insulin or by cells failing to respond to it. Without insulin action, cells take up little glucose, the liver keeps releasing glucose, and fat and protein are broken down for energy.
- Glycosuria: blood glucose rises above the renal threshold (about 180 mg dL−1), so the kidney cannot reabsorb all the filtered glucose and it appears in the urine.
- Polyuria and thirst: glucose in the filtrate holds water by osmosis, so a large volume of urine is produced and the person becomes dehydrated and always thirsty.
- Ketone bodies: fat is broken down so fast that the liver makes ketone bodies (e.g. acetoacetic acid, acetone). They make the blood acidic (ketoacidosis), especially in type 1, and can be life-threatening.
- Weight loss, tiredness and, in the long term, damage to blood vessels, eyes, kidneys and nerves.
Read more in the NIDDK (US National Institutes of Health) guide to diabetes.
Swipe the table sideways to see every column.
| Type 1 diabetes | Type 2 diabetes | |
|---|---|---|
| Older name | IDDM (insulin-dependent); also called early-onset diabetes | NIDDM (non-insulin-dependent); also called late-onset diabetes |
| Cause | Autoimmune destruction of β cells: the immune system (mainly T cells) attacks them, so little or no insulin is made | Target cells become resistant to insulin because they have too few insulin receptors or glucose transporters; insulin may be normal or high at first, but β cells may later fail |
| Usual onset | Childhood or early adulthood; often sudden | Usually adults over 40, but increasingly in young people; develops slowly |
| Proportion of cases | About 5 to 10% | About 90% |
| Risk factors | Family history and genes; a possible viral trigger | Obesity (especially abdominal fat), physical inactivity, diet high in sugar and refined carbohydrate, age, family history, some ethnic groups, diabetes in a previous pregnancy |
| Prevention | No known way to prevent it | Healthy body weight, regular exercise, a diet high in fibre and low in sugar and saturated fat |
| Treatment | Insulin (recombinant human insulin) by injection or pump, several times a day, matched to meals and blood glucose tests; replacing β cells with insulin-secreting cells grown from stem cells is being researched | Diet first: small, frequent meals instead of a few large ones, few sugary foods, starchy foods with a low glycaemic index and plenty of fibre to slow digestion; exercise and weight loss improve insulin action; then oral drugs such as metformin; insulin injections when these are not enough |
Diagnosis: the glucose tolerance test. After fasting, the person drinks a concentrated glucose solution and their blood glucose is measured at intervals. In a person with diabetes the concentration rises higher and takes much longer to fall back to normal.
Common mistakes
- Type 2 diabetics can and often do use insulin; diet and exercise are the first step, not the only one.
- An insulinoma is a tumour of β cells. The condition it causes, from too much insulin, is hypoglycaemia (low blood glucose).
Summary: the human endocrine system in eight points
- The human endocrine system is made of ductless glands that secrete hormones into the blood; only target cells with the right receptors respond.
- The hypothalamus links the nervous system and the endocrine system and controls the pituitary, which controls the thyroid, adrenal cortex and gonads.
- The thyroid sets the metabolic rate and heat production, and adrenaline from the adrenal medulla prepares the body for vigorous activity.
- Insulin and glucagon from the islets of Langerhans keep blood glucose near its set point: the best example of negative feedback in the endocrine system.
- Thyroxin, shivering, sweating, hair erection and changes in skin blood flow keep core body temperature close to 37 °C by negative feedback.
- Negative feedback keeps the endocrine system stable; positive feedback (oxytocin in childbirth, the LH surge) drives one-off events to completion.
- Water-soluble hormones act through membrane receptors and second messengers; steroid and thyroid hormones act through intracellular receptors and gene expression.
- Diabetes mellitus results when the β cells make too little insulin (type 1) or target cells respond poorly to it (type 2).
11 Common doubts about hormones and the endocrine system
These are the doubts students raise most often about the human endocrine system, with short answers.
What is the endocrine system?
The human endocrine system is the set of ductless glands and tissues that secrete hormones into the blood: the hypothalamus, pituitary, pineal, thyroid, parathyroids, thymus, adrenals, pancreatic islets and gonads, plus hormone-secreting cells in the heart, kidney and gut.
If hormones reach every cell in the body, why do only some cells respond?
Only target cells have the right receptor. Insulin can only affect a cell with insulin receptors, just as a radio signal is only heard by a radio tuned to that station. This is also why one hormone can have different effects in different tissues: the receptors and the pathways behind them differ. It is how the endocrine system can broadcast to the whole body yet act selectively.
Why is the pituitary called the master gland if the hypothalamus controls it?
Because its trophic hormones (TSH, ACTH, FSH, LH) control the thyroid, adrenal cortex and gonads. But the pituitary is itself under the command of the hypothalamus through releasing and inhibiting hormones, and of feedback from its target glands. ‘Master gland’ is a traditional name; the hypothalamus is really the boss of the endocrine system.
Are oxytocin and ADH pituitary hormones or hypothalamic hormones?
Both answers appear in books. They are made by neurosecretory cells in the hypothalamus and released from the posterior pituitary. In an exam question that asks which hormones are ‘released from’ or ‘stored in’ the posterior pituitary, the answer is oxytocin and ADH; if it asks where they are synthesised, the answer is the hypothalamus. IB does not ask you to compare how the anterior and posterior pituitary work (C3.1.13).
Glucose, glycogen, glucagon: which is which?
Glucose is the sugar in the blood. Glycogen is the polysaccharide store of glucose in liver and muscle. Glucagon is the hormone from α cells that tells the liver to break glycogen down. A useful trick: glucagon is what you need when glucose is gone.
If type 2 diabetics make insulin, why do some of them need insulin injections?
In type 2 diabetes the cells are resistant, so more insulin is needed for the same effect. At first the β cells make extra, but over years they often wear out and secretion falls. When diet, exercise and tablets can no longer keep blood glucose down, extra insulin overcomes the resistance. The MedlinePlus diabetes page explains the treatment options.
Why does diabetes make you pass so much urine and feel thirsty?
When blood glucose goes above the renal threshold (about 180 mg dL−1), the kidney tubules cannot reabsorb all the filtered glucose. The glucose left in the filtrate holds water by osmosis, so much more urine is produced (polyuria). The body loses water and the person feels very thirsty.
Is adrenaline a hormone or a neurotransmitter?
Adrenaline (epinephrine) secreted by the adrenal medulla into the blood is a hormone. Its close relative noradrenaline is mainly the neurotransmitter of sympathetic nerve endings, and is also secreted in small amounts as a hormone. The same kind of chemical can be a hormone or a neurotransmitter depending on how it is delivered: through the blood or across a synapse. The nervous system and the endocrine system share several of these chemicals.
Why does a lack of iodine make the thyroid bigger, when it makes less hormone?
The thyroid needs iodine to make T3 and T4. With too little iodine, hormone levels fall, so the hypothalamus and pituitary get less negative feedback and secrete more TRH and TSH. TSH keeps stimulating the thyroid to grow and work harder, and it enlarges into a goitre, but without iodine it still cannot make enough hormone. It is a neat example of endocrine system feedback going wrong.
Why does homeostasis rely on negative rather than positive feedback?
In the endocrine system, negative feedback opposes any change, so it brings a variable back towards its set point whether it has risen or fallen. Positive feedback reinforces a change, so the variable would keep moving away from the set point. That is useful only for events that must finish quickly, such as childbirth or ovulation.
Why does insulin have to be injected when thyroxine can be swallowed?
Steroid and thyroid hormones survive digestion and are absorbed from the gut, so thyroxine, cortisol-type drugs and contraceptive pills work by mouth. Insulin is a protein: proteases in the stomach and small intestine digest it before it can be absorbed, so it has to be injected (or given by a pump).
How is the endocrine system different from the nervous system?
The endocrine system sends hormones in the blood: its effects are slower, last longer and are often widespread. The nervous system sends impulses along neurons: fast, short-lived and aimed at particular cells.
Which hormone lowers blood glucose?
Insulin, from the β cells of the islets of Langerhans. Glucagon, adrenaline, cortisol and GH all raise it.
Which IB topics does this page cover?
C3.1 Integration of body systems (C3.1.3 hormonal and nervous signalling, C3.1.11 melatonin, C3.1.12 adrenaline, C3.1.13 hypothalamus and pituitary), D3.3 Homeostasis (D3.3.1 to D3.3.6 homeostasis, blood glucose, diabetes and thermoregulation, plus D3.3.10 ADH for HL), the hormones of D3.1 Reproduction, and for HL, C2.1 Chemical signalling. HL-only content is marked HL; everything else is SL.
12 Key terms
Many one-mark questions on the endocrine system test a definition.
Swipe the table sideways to see every column.
| Term | Meaning |
|---|---|
| Hormone | A chemical messenger secreted by an endocrine gland into the blood and carried to distant target cells, where it acts in small amounts. |
| Endocrine gland | A ductless gland of the endocrine system that secretes hormones into the blood. |
| Target cell | A cell with receptors for a particular hormone. |
| Ligand | The signalling chemical that binds to a receptor. |
| Neurosecretory cell | A neuron that secretes a hormone (e.g. in hypothalamic nuclei). |
| Portal vein | A vein that links two capillary beds, e.g. hypothalamus to anterior pituitary. |
| Trophic hormone | A hormone that stimulates another endocrine gland (TSH, ACTH, FSH, LH). |
| Negative feedback | A response that reverses the change that caused it. |
| Positive feedback | A response that increases the change that caused it. |
| Set point | The normal value around which a variable is kept. |
| Homeostasis | Keeping the internal environment (temperature, pH, blood glucose, osmotic concentration) within preset limits. |
| Circadian rhythm | A roughly 24-hour cycle in body activity, such as the sleep-wake cycle, set by the SCN. |
| Aquaporin | A channel protein that lets water cross a membrane; ADH adds aquaporins to collecting duct cells (HL). |
| Glycogenesis / glycogenolysis | Making glycogen from glucose / breaking glycogen down to glucose. |
| Gluconeogenesis | Making new glucose from non-carbohydrates such as amino acids and glycerol. |
| GLUT4 | The glucose transporter that insulin moves into the membrane of muscle and fat cells. |
| Second messenger | A molecule inside the cell (cAMP, IP3, Ca2+) that relays the signal from a membrane receptor. |
| Glycosuria | Glucose in the urine. |
| Catecholamines | Adrenaline and noradrenaline. |
13 Quick check
Tap each question to check what you know about the human endocrine system.
Test yourself on hormones and the endocrine system
1. What links the nervous system to the endocrine system?
The hypothalamus, which controls the pituitary gland.
2. Which gland of the endocrine system is called the master gland?
The pituitary gland.
3. Where are oxytocin and ADH made?
In neurosecretory cells of the hypothalamus; they are released from the posterior pituitary.
4. Name the four trophic hormones of the anterior pituitary.
FSH, LH, ACTH and TSH (FLAT).
5. Which hormone does the pineal gland secrete, and when?
Melatonin, mainly at night.
6. Which cells secrete glucagon?
α cells of the islets of Langerhans.
7. What does insulin move into the membranes of muscle and fat cells?
GLUT4 glucose transporters.
8. What is the second messenger made by adenylate cyclase?
Cyclic AMP (cAMP).
9. Name one example of positive feedback.
Oxytocin and uterine contractions during childbirth (or the LH surge).
10. What is the main cause of type 1 diabetes?
Autoimmune destruction of the β cells.
11. What causes simple goitre? (Beyond the syllabus)
Iodine deficiency.
12. Name the four homeostatic variables that IB lists for humans.
Body temperature, blood pH, blood glucose concentration and blood osmotic concentration.
13. Give three effects of adrenaline that help vigorous activity.
Any three: faster heart rate, wider airways and faster ventilation, glycogen broken down to glucose, blood redirected from the gut and kidneys to skeletal muscle and liver.
14. Which part of the brain is the master clock for circadian rhythms?
The suprachiasmatic nuclei (SCN) of the hypothalamus.
15. Which hormone raises the metabolic rate when the body is cold?
Thyroxin, released when TRH from the hypothalamus triggers TSH release from the pituitary.
16. HL: What does ADH do to cells of the collecting duct?
It makes vesicles containing aquaporins fuse with the plasma membrane, so more water is reabsorbed.
17. What is the physiological change behind type 2 diabetes?
Target cells respond poorly to insulin because they have too few insulin receptors or glucose transporters.
Related IB Biology chapters
The endocrine system works with almost every other body system. Continue with these IB chapters:
- Integration of Body Systems: the rest of C3.1, from the brain and spinal cord to the control of heart rate and ventilation.
- Nervous System and Neural Control: nerve impulses and synapses, the other half of coordination.
- Blood, Heart and Circulation: how adrenaline and the nervous system change heart rate and blood supply.
- Cell Membrane: glycoproteins and cell recognition: the receptor proteins that hormones bind.
- Membrane Transport (IB Biology): diffusion, osmosis and active transport behind glucose uptake.
- Gas Exchange: control of ventilation: breathing and the blood gases.
- IB Biology topics: every IB topic on this site, including C2.1 and D3.3.
© competitorspoint.com · Biology notes. Labelled flow diagrams are original to competitorspoint.com.