Blood, Heart and Circulation
Blood is a fluid connective tissue made of plasma and formed elements: red blood cells, white blood cells and platelets. The heart is a four-chambered muscular pump that drives blood through a double circulation, the pulmonary circuit to the lungs and the systemic circuit to the rest of the body, carrying oxygen, nutrients, hormones and wastes.
Blood and its cells, blood groups and clotting, the structure of the heart and blood vessels, the cardiac cycle and ECG, double circulation, blood pressure and lymph, for IB Biology and NEET. HL-only content is marked.
1 Components and functions of blood
Syllabus link: NCERT XI Ch 15 Body Fluids and Circulation, 15.1 Blood (15.1.1 Plasma, 15.1.2 Formed elements); IB B3.2 Transport (first assessment 2025)
NCERT = statement as given in NCERT (use in NEET/CBSE answers) IB = IB Biology (first assessment 2025) link HL = IB Higher Level only
Every cell needs a steady supply of oxygen and food and a way to get rid of waste. In tiny animals diffusion is enough. In large animals like us, a pump and a set of pipes are needed. This chapter on the heart and circulation covers the fluid (blood and lymph), the pump (the heart) and the pipes (blood vessels), and how the whole system is controlled. It is card 3 of our Human Physiology series, after Digestion and Absorption and Gas Exchange.
Key points
- Blood is a fluid connective tissue: plasma (about 55%) plus formed elements (about 45%).
- The human heart has four chambers and pumps blood through two circuits: double circulation.
- One cardiac cycle takes 0.8 s at 72 beats per minute; cardiac output is about 5 L per minute.
- ABO and Rh blood groups decide who can safely give blood to whom.
- Tissue fluid that is not returned to capillaries drains into lymph vessels and back into the veins.
What does the circulatory system do?
The circulatory system is the transport system of the body. It carries:
- gases: oxygen from the lungs to the tissues and carbon dioxide back;
- nutrients: glucose, amino acids and fats from the gut;
- nitrogenous wastes: urea from the liver to the kidneys;
- hormones from endocrine glands to their target organs;
- antibodies and white blood cells to sites of infection.
It also spreads heat around the body, helps keep the pH steady, and seals wounds by clotting. In an exam, if the options list all of these, the answer is “all of the above”.
Open and closed circulatory systems
Animals move body fluid in one of two ways. In an open system, the heart pumps blood into open spaces or body cavities (sinuses), so the tissues are bathed directly in blood (called haemolymph). Blood does not stay inside vessels, so it flows slowly and at low pressure. In a closed system, blood always stays inside a network of vessels, so it can be pushed faster and its flow can be directed precisely.
Swipe the table sideways to see every column.
| Type | Found in | Features |
|---|---|---|
| Open | Arthropods, most molluscs, tunicates; echinoderms have a reduced, open (haemal) system | Blood leaves vessels into sinuses; tissues bathed directly; slow flow, low pressure |
| Closed | Annelids (earthworm), cephalopod molluscs (octopus, squid), all vertebrates | Blood always inside vessels; faster flow; flow can be regulated |
NCERT NCERT: open circulatory systems are present in arthropods and molluscs, and annelids and chordates have a closed circulatory system. Leeches are the annelid exception often quoted in MCQs: their true vessels are reduced and blood flows through haemocoelic channels. Among the usual MCQ options, the annelids are the first group with a true closed system (the ribbon worms, phylum Nemertea, have a simpler one).
Body fluids: blood and lymph
NCERT Blood is the most common body fluid in higher organisms. Lymph is the other. Blood is a special connective tissue: a fluid matrix called plasma with formed elements (cells and cell fragments) suspended in it.
Plasma
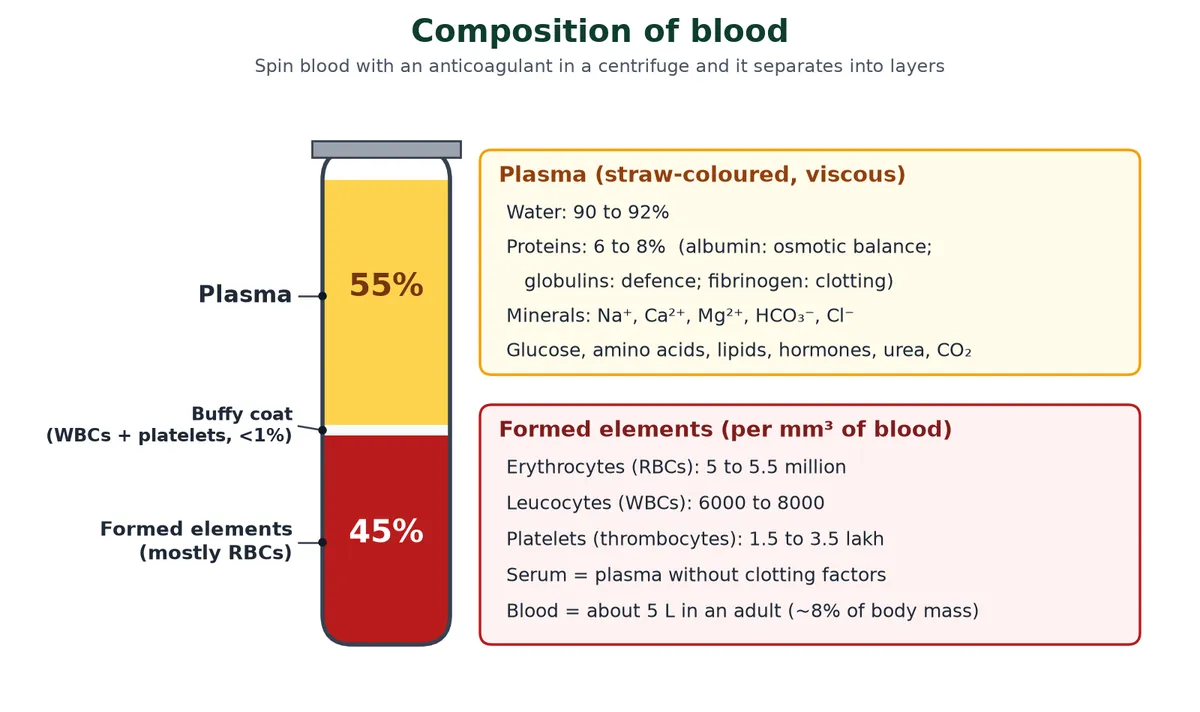
Plasma is a straw-coloured, viscous fluid that makes up nearly 55% of blood. NCERT 90 to 92% of plasma is water and proteins make up 6 to 8%.
Swipe the table sideways to see every column.
| Plasma protein | Main function |
|---|---|
| Fibrinogen | Needed for clotting (coagulation) |
| Globulins | Defence: antibodies are gamma globulins |
| Albumins | Osmotic balance: they keep water inside blood vessels |
Plasma also carries small amounts of minerals (Na+, Ca2+, Mg2+, HCO3–, Cl–), glucose, amino acids, lipids, hormones, urea and dissolved CO2. Clotting factors are also present in plasma, in an inactive form. Plasma without the clotting factors is called serum.
Formed elements
Erythrocytes (red blood cells), leucocytes (white blood cells) and platelets together are the formed elements. They make up nearly 45% of blood. The next section looks at each one.
Exam traps
- Serum = plasma minus clotting factors (mainly fibrinogen). It is not ‘blood without cells’.
- Albumin is the most abundant plasma protein and is the one that maintains osmotic pressure.
- Blood is a connective tissue, even though it is a liquid, because it develops from mesoderm and has a matrix (plasma).
2 Red blood cells, white blood cells and platelets
Syllabus link: NCERT XI 15.1.2 Formed elements; IB B3.2 (transport), C3.2 Defence against disease (phagocytes, lymphocytes)
Three kinds of formed elements do the work of blood in the heart and circulation system: red cells carry gases, white cells defend, and platelets seal leaks.
Red blood cells (erythrocytes)
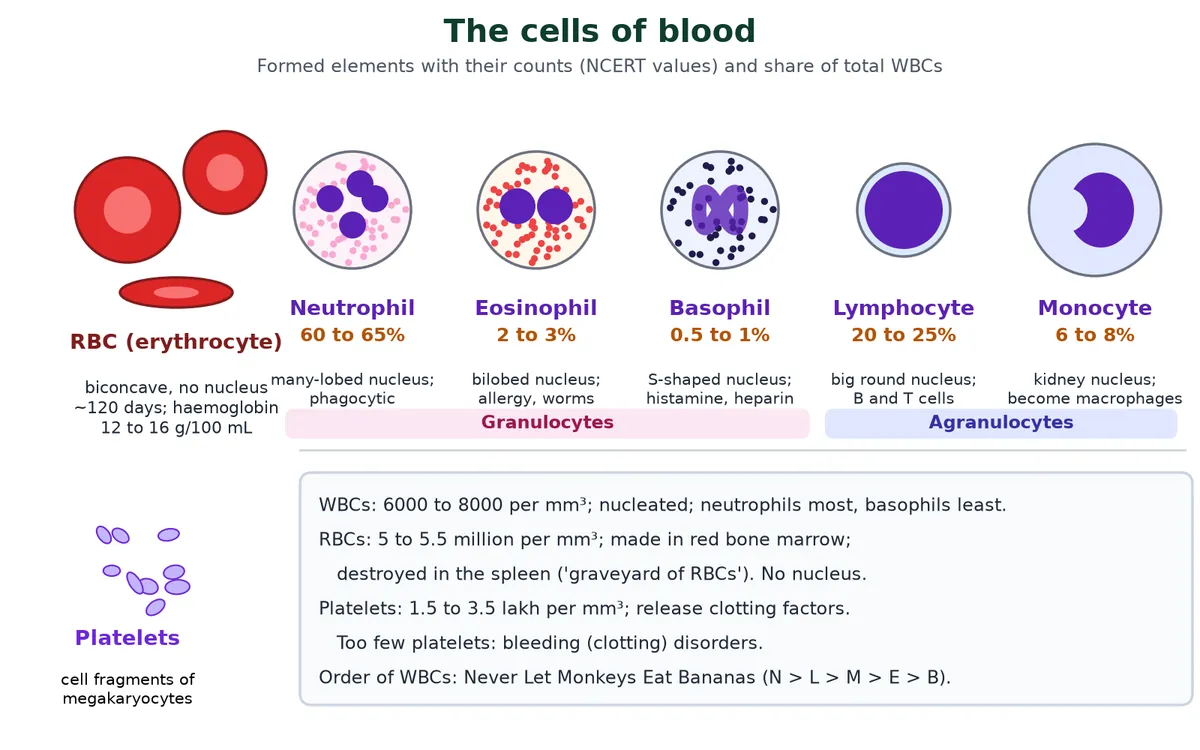
Erythrocytes are the most abundant cells in blood: NCERT a healthy adult has 5 to 5.5 million RBCs per mm3 of blood. They are made in the red bone marrow in adults, from haematopoietic stem cells. In most mammals they have no nucleus and are biconcave, which gives a large surface for gas exchange and room for more haemoglobin.
- They contain the red iron-containing protein haemoglobin: about 12 to 16 g in every 100 mL of blood in a healthy person. Haemoglobin carries most of the oxygen (and some CO2).
- An average RBC lives about 120 days, after which it is destroyed in the spleen, the ‘graveyard of RBCs’. The liver recycles the iron and turns the haem into bile pigment.
- Without a nucleus and mitochondria an RBC cannot divide, but it also does not use up the oxygen it carries.
White blood cells (leucocytes): a short summary
Leucocytes are colourless because they have no haemoglobin. They are nucleated, relatively fewer in number (NCERT 6000 to 8000 per mm3) and generally short-lived. There are two main groups:
Swipe the table sideways to see every column.
| Group | Cell | Share of WBCs | Key role |
|---|---|---|---|
| Granulocytes | Neutrophils | 60 to 65% (most abundant) | Phagocytosis of bacteria and foreign organisms |
| Granulocytes | Eosinophils | 2 to 3% | Resist infections; linked to allergic reactions |
| Granulocytes | Basophils | 0.5 to 1% (least abundant) | Secrete histamine, serotonin and heparin; inflammation |
| Agranulocytes | Lymphocytes | 20 to 25% | B and T lymphocytes: the immune response |
| Agranulocytes | Monocytes | 6 to 8% | Phagocytic; become macrophages in tissues |
This is only a summary. For the structure of each cell, how they fight infection, and NEET-style questions on them, read our full guide to white blood cells and their functions.
Platelets (thrombocytes)
Platelets are not whole cells. NCERT They are cell fragments produced from megakaryocytes, special cells in the bone marrow. Blood normally has 1,50,000 to 3,50,000 platelets per mm3. Platelets release a variety of substances that are involved in clotting. A fall in their number can lead to clotting disorders, which cause excessive loss of blood from the body.
Swipe the table sideways to see every column.
| Formed element | Count per mm3 | Nucleus | Life span | Main job |
|---|---|---|---|---|
| RBC | 5 to 5.5 million | Absent (mammals) | About 120 days | Carry O2 (and some CO2) |
| WBC | 6000 to 8000 | Present | Hours to years (most are short-lived) | Defence |
| Platelet | 1.5 to 3.5 lakh | Absent (fragment) | About 7 to 10 days | Clotting |
Click to check: which white blood cell is most common, and which is least?
Neutrophils are the most common (60 to 65%); basophils are the least (0.5 to 1%). Memory hook for the order: Never Let Monkeys Eat Bananas (neutrophils > lymphocytes > monocytes > eosinophils > basophils).
3 Blood groups and blood clotting
Syllabus link: NCERT XI 15.2 Blood Groups (15.2.1 ABO, 15.2.2 Rh), 15.3 Coagulation of Blood; IB C3.2.2 sealing cuts in skin by blood clotting; IB D3.2 (ABO multiple alleles, codominance)
Two practical questions come up whenever blood leaves the heart and circulation: can it be given to someone else, and how does the body stop it leaking out?
ABO grouping
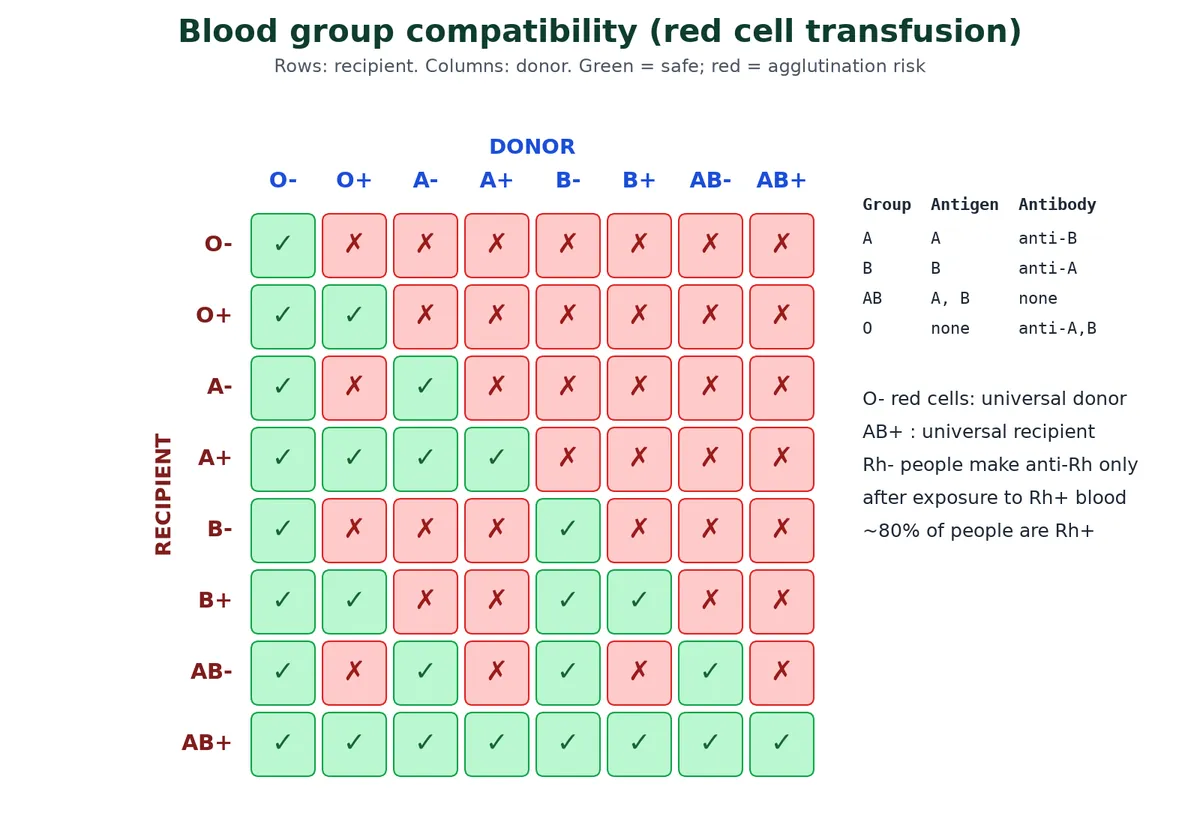
Blood of different people can look the same but may not mix safely. NCERT ABO grouping is based on the presence or absence of two surface antigens (chemicals that can induce an immune response) on the RBCs, namely A and B. The plasma of different people contains two natural antibodies (proteins made in response to antigens): anti-A and anti-B. Karl Landsteiner discovered the ABO system in 1900.
NCERT Table 15.1 Blood groups and donor compatibility
Swipe the table sideways to see every column.
| Blood group | Antigens on RBCs | Antibodies in plasma | Donor’s group |
|---|---|---|---|
| A | A | anti-B | A, O |
| B | B | anti-A | B, O |
| AB | A, B | nil | AB, A, B, O |
| O | nil | anti-A, B | O |
If a person receives red cells carrying an antigen that their own plasma has antibodies against, the donor cells clump together (agglutination) and burst. This can block small vessels and damage the kidneys. That is why blood is matched before every transfusion.
- Group O people are universal donors: their red cells carry neither A nor B antigen.
- Group AB people are universal recipients: their plasma has neither anti-A nor anti-B.
- IB Genetics link: the ABO gene has three alleles, IA, IB and i. IA and IB are codominant and both are dominant to i, so there are six genotypes but four phenotypes.
Try it: blood group compatibility checker
Tap a patient’s blood group to see whose red cells they can safely receive.
Patient O−: antigens on red cells: none; antibodies in plasma: anti-A and anti-B; has no Rh antigen, so must not get Rh+ red cells.
Can receive red cells fromO−
Can give red cells toO−O+A−A+B−B+AB−AB+
Patient O+: antigens on red cells: none; antibodies in plasma: anti-A and anti-B; has the Rh (D) antigen.
Can receive red cells fromO−O+
Can give red cells toO+A+B+AB+
Patient A−: antigens on red cells: A; antibodies in plasma: anti-B; has no Rh antigen, so must not get Rh+ red cells.
Can receive red cells fromO−A−
Can give red cells toA−A+AB−AB+
Patient A+: antigens on red cells: A; antibodies in plasma: anti-B; has the Rh (D) antigen.
Can receive red cells fromO−O+A−A+
Can give red cells toA+AB+
Patient B−: antigens on red cells: B; antibodies in plasma: anti-A; has no Rh antigen, so must not get Rh+ red cells.
Can receive red cells fromO−B−
Can give red cells toB−B+AB−AB+
Patient B+: antigens on red cells: B; antibodies in plasma: anti-A; has the Rh (D) antigen.
Can receive red cells fromO−O+B−B+
Can give red cells toB+AB+
Patient AB−: antigens on red cells: A,B; antibodies in plasma: none; has no Rh antigen, so must not get Rh+ red cells.
Can receive red cells fromO−A−B−AB−
Can give red cells toAB−AB+
Patient AB+: antigens on red cells: A,B; antibodies in plasma: none; has the Rh (D) antigen.
Can receive red cells fromO−O+A−A+B−B+AB−AB+
Can give red cells toAB+
Red cell (packed cell) transfusion only. Plasma follows the reverse rule, and real transfusions are always cross-matched.
Rh grouping
NCERT Another antigen, the Rh antigen, similar to one present in Rhesus monkeys (hence Rh), is also observed on the surface of RBCs of the majority (nearly 80%) of humans. Such people are Rh positive (Rh+), and those without it are Rh negative (Rh−). An Rh− person does not have anti-Rh antibodies naturally; they make them only after being exposed to Rh+ blood. So Rh grouping must also be done before a transfusion.
Erythroblastosis foetalis (Rh incompatibility in pregnancy)
- An Rh− mother carries an Rh+ foetus (the father is Rh+). In the first pregnancy the placenta keeps the two bloods separate, so the first baby is usually safe.
- During delivery of the first child, a small amount of the baby’s Rh+ blood can enter the mother’s blood. She starts making anti-Rh antibodies.
- In a later pregnancy with an Rh+ foetus, these antibodies cross the placenta and destroy the foetal red blood cells.
- This can be fatal to the foetus or cause severe anaemia and jaundice in the baby: erythroblastosis foetalis.
- NCERT It can be avoided by giving the mother anti-Rh antibodies (anti-D immunoglobulin) immediately after the delivery of the first child. They remove the baby’s Rh+ cells before her immune system responds.
Coagulation of blood
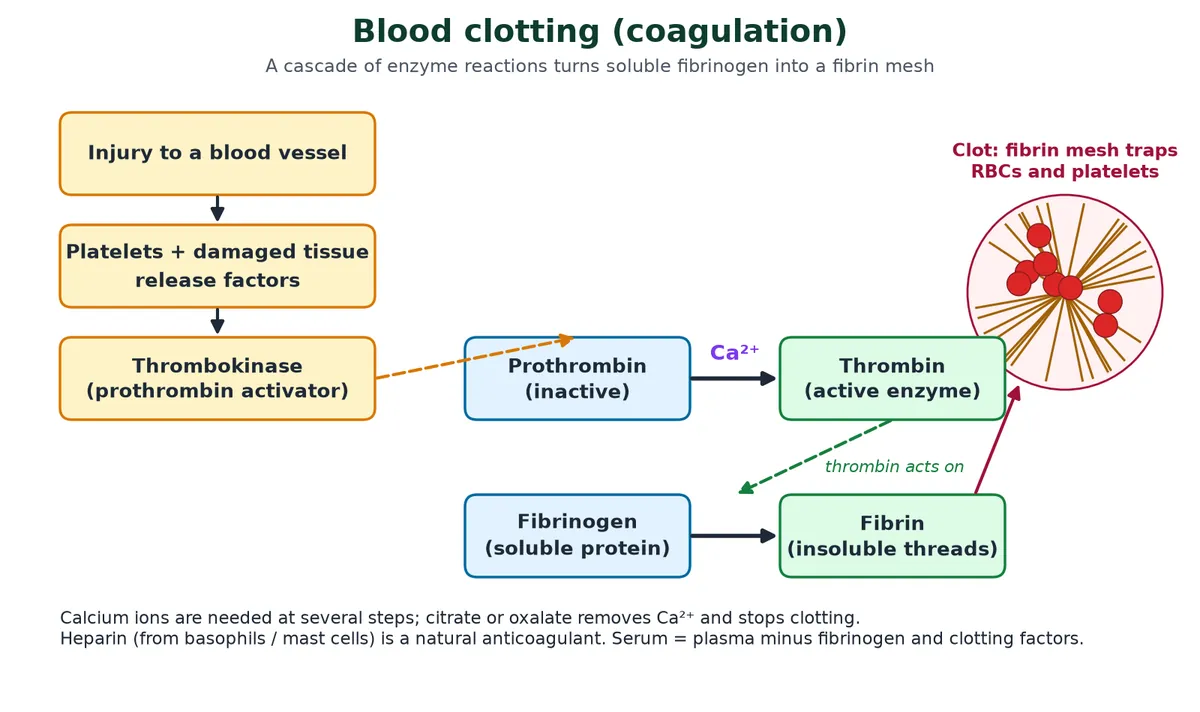
When you cut yourself, bleeding usually stops within a few minutes. NCERT Blood shows coagulation (clotting) in response to an injury or trauma: a mechanism that prevents excessive loss of blood from the body. A dark reddish-brown scum forms at the site of the cut. This is a clot or coagulum, formed mainly of a network of threads called fibrin in which dead and damaged formed elements of blood are trapped.
- An injury exposes the tissue under the vessel lining. Platelets stick to the damaged area and to each other, forming a temporary platelet plug.
- Platelets and the damaged tissue release clotting factors. A cascade of linked enzyme reactions follows, involving many factors present in plasma in an inactive state.
- These reactions form thrombokinase (the prothrombin activator).
- Thrombokinase converts inactive prothrombin into the active enzyme thrombin. Calcium ions play a very important role here.
- Thrombin converts soluble fibrinogen into insoluble fibrin threads.
- The fibrin mesh traps blood cells and platelets, and the clot seals the wound. Later the clot shrinks and serum is squeezed out.
IB IB C3.2.2 expects you to outline this in three steps: platelets release clotting factors; a cascade of reactions leads to the rapid formation of thrombin; thrombin converts fibrinogen to fibrin, which forms a mesh that traps cells. The cascade lets a few platelets set off a large response quickly, but it has to be tightly controlled: a clot inside a coronary artery (a thrombus) causes a heart attack.
Why stored blood does not clot
- Blood banks add sodium citrate or oxalate. These remove Ca2+ ions, and without calcium the cascade stops.
- Heparin, released by basophils and mast cells, is a natural anticoagulant that blocks thrombin.
- Inside healthy vessels, the smooth endothelium releases substances that keep platelets from sticking, so clotting normally starts only at an injury.
4 Structure of the heart and blood vessels
Syllabus link: NCERT XI 15.5.1 Human Circulatory System (heart, blood vessels); IB B3.2.1 to B3.2.5 (capillaries, arteries, veins, pulse) and B3.2.14 HL (adaptations of the mammalian heart)
The heart is the pump at the centre of the heart and circulation system; the blood vessels are the pipes. Structure matches function in both.
Position and coverings of the heart
NCERT The heart, the mesodermally derived organ, is situated in the thoracic cavity, in between the two lungs, slightly tilted to the left. It has the size of a clenched fist. It sits in a hollow of the left lung called the cardiac notch, protected by the rib cage. It is protected by a double-walled membranous bag, the pericardium, enclosing the pericardial fluid, which reduces friction as the heart beats.
From outside to inside, the wall and its coverings are:
- Fibrous pericardium: tough outer sac that anchors the heart.
- Parietal pericardium: outer serous layer, lining the fibrous sac.
- Pericardial fluid in the pericardial cavity, secreted by the two serous layers.
- Visceral pericardium (epicardium): inner serous layer, stuck to the heart.
- Myocardium: thick layer of cardiac muscle.
- Endocardium: thin endothelium (squamous epithelium) lining the chambers and valves.
Cardiac muscle is striated, branched and involuntary. Each cell usually has one central nucleus. Cells are joined end to end by intercalated discs containing gap junctions, so ions and electrical impulses pass quickly from cell to cell and the heart contracts as one unit. Cardiac muscle never tires because it has many mitochondria and a rich blood supply.
Chambers and septa
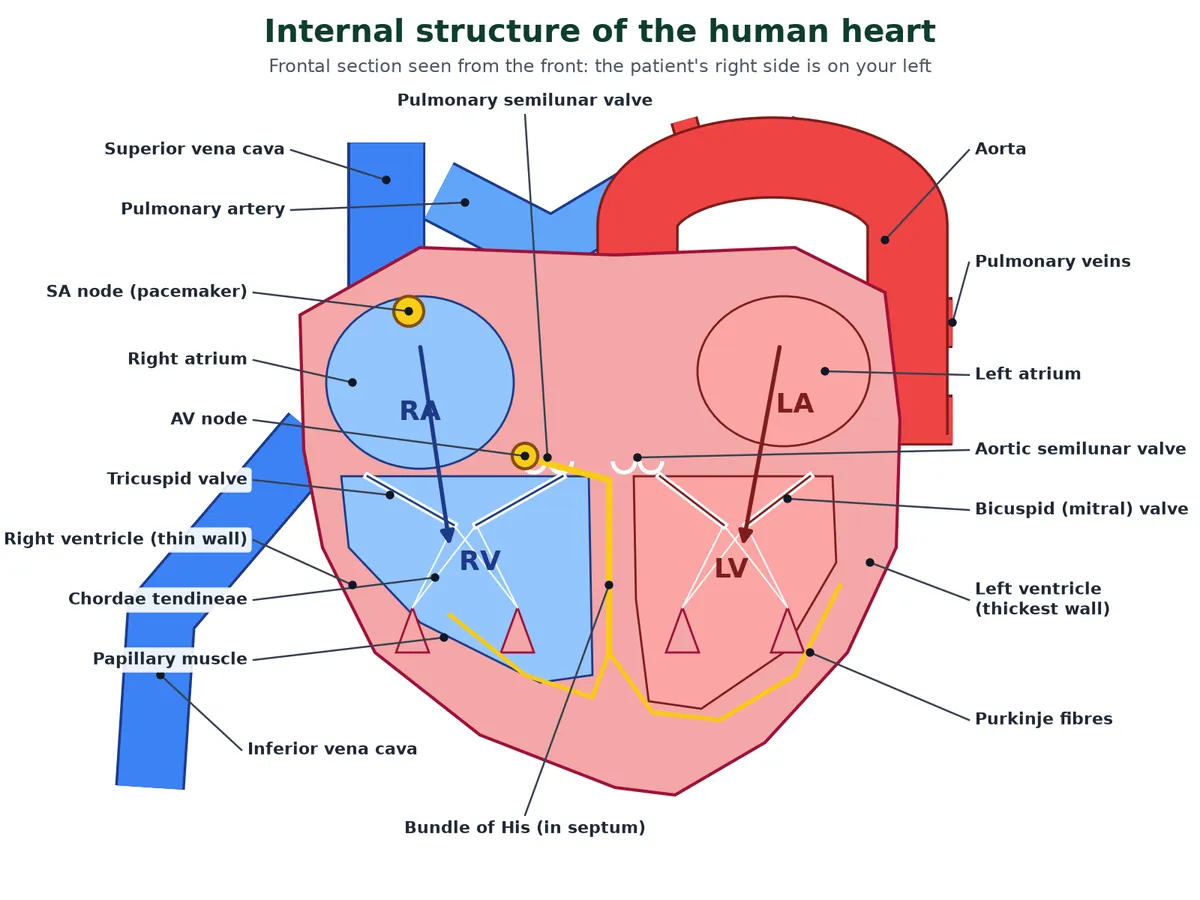
NCERT Our heart has four chambers: two relatively small upper chambers called atria and two larger lower chambers called ventricles. A thin, muscular wall called the inter-atrial septum separates the right and the left atrium, whereas a thick-walled inter-ventricular septum separates the left and the right ventricle. The atrium and the ventricle of the same side are separated by a thick fibrous tissue called the atrio-ventricular septum, which has an opening with a valve.
Auricle or atrium? In a whole-heart drawing, the ear-like flap on each atrium is the auricle (auricle means ‘little ear’). In a longitudinal section, the same region appears as a hollow chamber, the atrium. Many books use the words as synonyms.
Valves
Swipe the table sideways to see every column.
| Valve | Where | Prevents backflow from |
|---|---|---|
| Tricuspid (three cusps) | Between right atrium and right ventricle | Right ventricle to right atrium |
| Bicuspid or mitral (two cusps) | Between left atrium and left ventricle | Left ventricle to left atrium |
| Pulmonary semilunar | Opening of the pulmonary artery | Pulmonary artery to right ventricle |
| Aortic semilunar | Opening of the aorta | Aorta to left ventricle |
| Eustachian valve | Opening of the inferior vena cava into the right atrium | (guides blood in the foetus; small in adults) |
| Thebesian valve | Opening of the coronary sinus into the right atrium | Right atrium to coronary sinus |
NCERT The valves in the heart allow the flow of blood only in one direction: from the atria to the ventricles and from the ventricles to the pulmonary artery or aorta. The opening of the superior vena cava and the four pulmonary veins have no valves.
Inside the chambers
- Right atrium receives deoxygenated blood from the superior vena cava, the inferior vena cava and the coronary sinus (blood from the heart muscle itself). Its wall has low muscular ridges called musculi pectinati.
- On the inter-atrial septum there is an oval depression, the fossa ovalis. It is the remains of the foramen ovale, an opening that lets blood pass from the right to the left atrium in the foetus (whose lungs do not work); it closes after birth.
- Left atrium receives oxygenated blood from the lungs through four pulmonary veins, two from each lung.
- Ventricles are the pumping (distributing) chambers. Their inner walls carry muscular ridges called columnae carneae (trabeculae carneae); some project as papillary muscles.
- Chordae tendineae are tendon-like cords joining the papillary muscles to the cusps of the AV valves. When the ventricles contract, the papillary muscles pull on them and stop the cusps from turning inside out into the atria. Chain: columnae carneae → papillary muscles → chordae tendineae → AV valve.
- The left ventricle has the thickest wall, because it pumps blood all round the body against high resistance; the right ventricle pumps only to the nearby lungs.
HL Adaptations of the mammalian heart (B3.2.14)
- Cardiac muscle contracts without nervous stimulation (myogenic) and does not fatigue.
- The SA node acts as a pacemaker; the AV node delays the impulse so the atria empty before the ventricles contract.
- AV valves and semilunar valves keep flow one way; chordae tendineae stop the AV valves inverting.
- A septum keeps oxygenated and deoxygenated blood apart.
- The thick left ventricle wall produces high pressure for the systemic circulation.
- Coronary vessels supply the heart muscle with oxygen and glucose.
Blood vessels: arteries, veins and capillaries
Blood leaves the heart in arteries and returns in veins. The order is: aorta → arteries → arterioles → capillaries → venules → veins → venae cavae. Arteries carry blood away from the heart and veins carry it towards it, whether it is oxygenated or not; that is why the pulmonary artery carries deoxygenated blood.
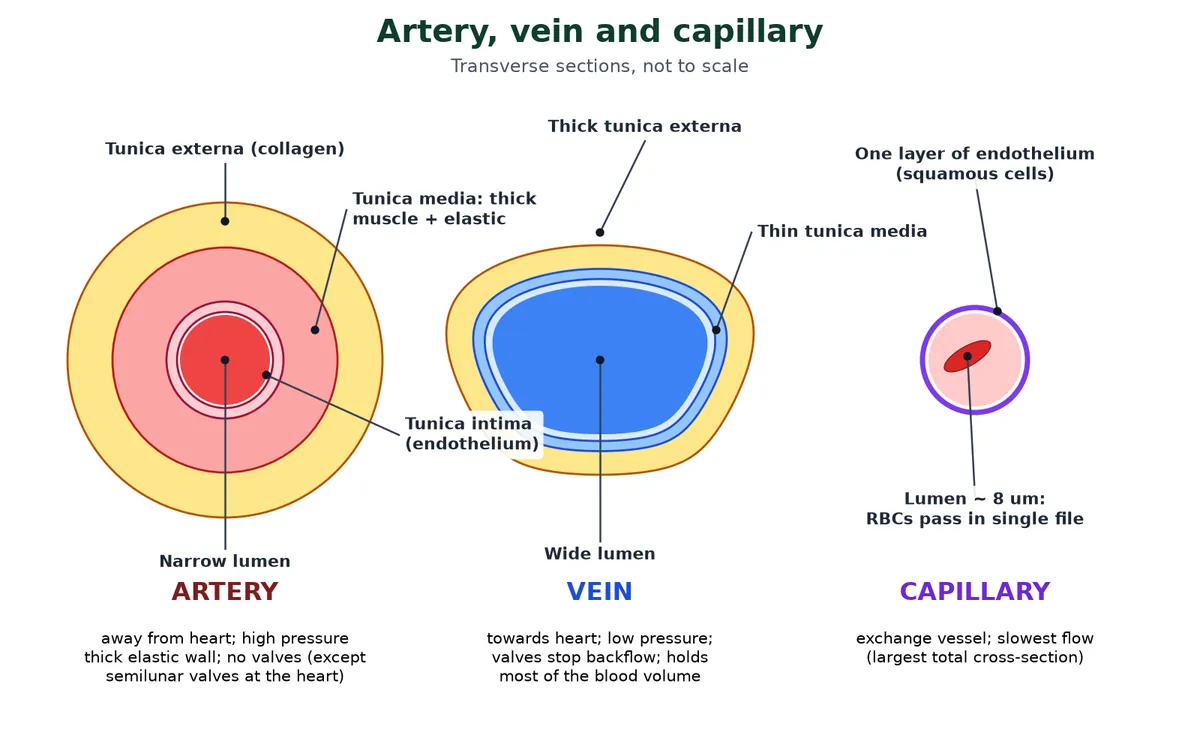
Arteries and veins have three layers: an inner tunica intima (endothelium of squamous cells over elastic tissue), a middle tunica media (smooth muscle and elastic fibres) and an outer tunica externa (mainly collagen fibres). Capillaries have only the endothelium.
Swipe the table sideways to see every column.
| Feature | Artery | Vein | Capillary |
|---|---|---|---|
| Direction | Away from heart | Towards heart | Links arterioles to venules |
| Pressure | High, pulsing | Low, steady | Falling |
| Wall | Thick; thick tunica media with elastic and muscle fibres | Thin; thin media, relatively thicker externa | One cell thick (endothelium only) |
| Lumen | Narrow | Wide | About 5 to 10 µm: RBCs pass one at a time |
| Valves | None (except semilunar valves at the heart) | Present, especially in the limbs | None |
| Blood held | About 15% | About 60 to 65% (blood reservoir) | About 5% |
IB IB B3.2.1 to B3.2.5 links each structure to its job:
- Capillaries: a very large total surface area, a wall one cell thick and, in organs such as the kidney and small intestine, fenestrations (pores) let substances exchange quickly with tissue fluid.
- Arteries: elastic fibres stretch when the ventricle pushes blood in and recoil between beats, which keeps blood moving and evens out the pressure; muscle in the wall resists bursting and can narrow the lumen (vasoconstriction) to control flow.
- Veins: pressure is too low to push blood up the legs, so valves stop backflow and the squeezing of nearby skeletal muscles pushes blood towards the heart.
- Pulse rate: each surge of blood in an artery can be felt as a pulse at the wrist (radial artery) or neck (carotid artery). Count beats for 30 s and double, or use a digital monitor.
Why does blood slow down in capillaries?
Resistance to flow rises steeply as a vessel narrows: it is proportional to 1/r4 (r = radius). Most of the peripheral resistance is in the arterioles, whose muscular walls can change their radius; this is where blood pressure drops the most. Each capillary is narrower still, but there are billions of them side by side, so their total cross-sectional area is about 1000 times that of the aorta. The same volume of blood spread over a much wider bed moves slowly (about 0.03 cm/s), which gives time for exchange.
Major arteries from the aorta
Swipe the table sideways to see every column.
| Part of aorta | Branch | Supplies |
|---|---|---|
| Ascending aorta | Right and left coronary arteries | Heart muscle (myocardium) |
| Arch of aorta | Brachiocephalic (innominate) artery → right common carotid + right subclavian | Right side of head and neck; right arm |
| Arch of aorta | Left common carotid | Left side of head and brain |
| Arch of aorta | Left subclavian | Left arm |
| Descending (thoracic and abdominal) aorta | Phrenic; coeliac (hepatic, gastric, splenic branches); renal; gonadal; superior and inferior mesenteric; common iliac | Diaphragm; liver, stomach, spleen; kidneys; testes or ovaries; small and large intestine; legs |
Blood from the head and brain returns in the jugular veins, from the arms in the subclavian veins; these join to form the superior vena cava. The inferior vena cava collects blood from the lower body. For a clear animation of the route through the heart, see the US National Heart, Lung, and Blood Institute page on how blood flows through the heart.
5 Cardiac cycle and regulation of heart rate
Syllabus link: NCERT XI 15.5.1 (nodal tissue), 15.5.2 Cardiac Cycle, 15.5.3 Electrocardiograph (ECG), 15.7 Regulation of Cardiac Activity; IB B3.2.15 HL (stages of the cardiac cycle), C3.1 HL (control of heart rate by the medulla)
Every heartbeat follows the same cardiac cycle of contraction and relaxation. This section covers how the beat starts, the stages of the cardiac cycle, heart sounds, the ECG, and how the heart rate is controlled.
A heart that starts its own beat
A heart is myogenic when the impulse for each beat starts in the heart muscle itself, and neurogenic when it comes from nerves (ganglia) outside the muscle. Vertebrate hearts, including ours, and the hearts of molluscs (cephalopods such as the octopus are the usual exam example) are myogenic. Many arthropods (such as crabs and lobsters) and annelids have neurogenic hearts. A myogenic heart keeps beating for a while even when removed from the body.
Nodal tissue: the conducting system
NCERT A specialised cardiac musculature called the nodal tissue is distributed in the heart:
- Sino-atrial node (SAN): a patch in the right upper corner of the right atrium, near the opening of the superior vena cava. It makes the most action potentials, about 70 to 75 per minute, so it sets the rhythm: it is the pacemaker.
- Three internodal pathways (anterior, middle and posterior) carry the impulse across the right atrium to the AV node, while it also spreads over both atria.
- Atrio-ventricular node (AVN): in the lower left corner of the right atrium, close to the atrio-ventricular septum and the opening of the coronary sinus. It delays the impulse by about 0.1 s so the atria finish emptying before the ventricles contract.
- AV bundle (bundle of His): a single bundle that passes from the AV node through the atrio-ventricular septum into the top of the inter-ventricular septum. There it divides into right and left bundle branches, which run down the septum.
- Purkinje fibres: the branches end in a network of fibres spreading through the walls of both ventricles, from the apex upwards, so the ventricles contract from the bottom and squeeze blood up into the arteries.
Speeds are very different along this path: about 0.05 m/s in the AV node (the delay), about 0.3 to 1 m/s in atrial muscle, and up to about 4 m/s in Purkinje fibres, the fastest in the heart.
Action potential in heart muscle
- Resting (polarised) state: outside of the membrane positive, inside negative. Resting potential is about −90 mV in ventricular muscle (about −60 mV in SA node cells). It is measured in millivolts, displayed on a cathode ray oscilloscope (CRO).
- Depolarisation: Na+ ions rush in and the inside becomes positive. This happens just before the muscle fibre contracts.
- Repolarisation: K+ ions move out (efflux) and the inside becomes negative again.
- The sodium-potassium pump restores the original ion distribution: it pumps 3 Na+ out and 2 K+ in for each ATP used.
- SA node cells have no stable resting potential; they slowly depolarise on their own until they fire. That is what makes them a pacemaker.
The cardiac cycle
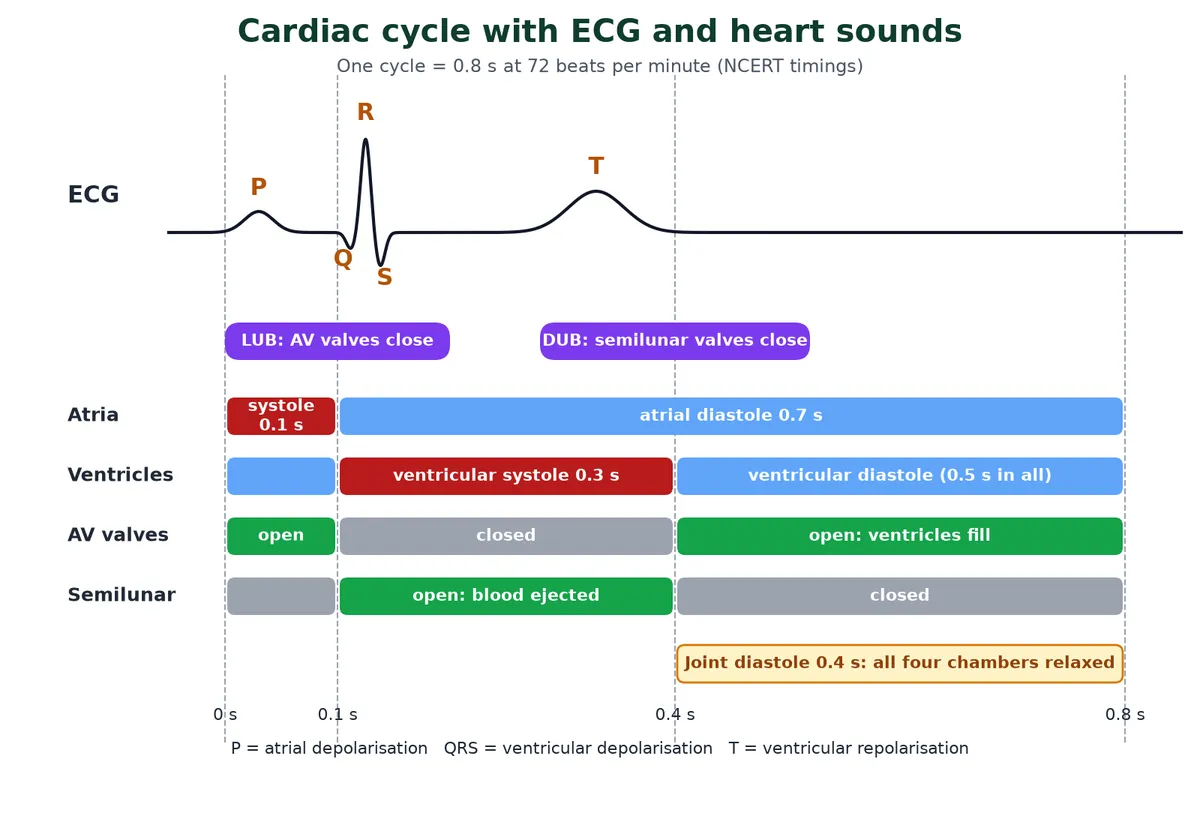
NCERT The sequential events in the heart which are cyclically repeated are called the cardiac cycle; it consists of systole (contraction) and diastole (relaxation) of both the atria and ventricles. The heart beats about 72 times per minute, so one cycle lasts 60/72 = about 0.8 s.
Step through one heartbeat
Step 1 of 5: Joint diastole 0.4 s
All four chambers are relaxed. Blood flows from the venae cavae and pulmonary veins into the atria and, because the AV valves are open, straight on into the ventricles. About 70% of ventricular filling happens now, passively. The first third of filling is rapid, the middle third is slow (diastasis).
Step 2 of 5: Atrial systole 0.1 s
The SA node fires and a wave of contraction spreads over both atria (ECG: P wave). The atria squeeze the last of their blood into the ventricles, adding about 30% to ventricular filling. Both AV valves (tricuspid and bicuspid) are open.
Step 3 of 5: Ventricular systole begins: isovolumetric contraction ~0.05 s
The impulse passes through the AV node, bundle of His and Purkinje fibres (ECG: QRS). The ventricles contract. Pressure in them rises above atrial pressure, so the AV valves close: the first heart sound, lub. For a moment all four valves are shut, so volume does not change while pressure climbs.
Step 4 of 5: Ventricular ejection rest of the 0.3 s
When ventricular pressure exceeds the pressure in the aorta and pulmonary artery, the semilunar valves open and blood is pushed out: about 70 mL from each ventricle (stroke volume). Meanwhile the atria relax and start filling again. The ventricles repolarise (ECG: T wave).
Step 5 of 5: Ventricular diastole begins: isovolumetric relaxation start of the 0.4 s
The ventricles relax, their pressure falls below that in the arteries, and the semilunar valves snap shut: the second heart sound, dub. When ventricular pressure drops below atrial pressure, the AV valves open and the cycle returns to joint diastole.
Swipe the table sideways to see every column.
| Phase | Duration | What happens |
|---|---|---|
| Atrial systole | 0.1 s | Atria contract; ventricles in diastole |
| Ventricular systole | 0.3 s | Ventricles contract; atria relax and refill |
| Joint (complete) diastole | 0.4 s | All chambers relax; passive filling |
| Total atrial diastole | 0.7 s | 0.3 s of ventricular systole + 0.4 s joint diastole |
| Total ventricular diastole | 0.5 s | 0.1 s of atrial systole + 0.4 s joint diastole |
Heart sounds
Swipe the table sideways to see every column.
| Sound | Cause | Timing and nature |
|---|---|---|
| First, lub (S1) | Closure of the AV (tricuspid and bicuspid) valves | Start of ventricular systole; low-pitched, longer (about 0.15 s) |
| Second, dub (S2) | Closure of the semilunar valves | Start of ventricular diastole; sharper, shorter (about 0.1 s) |
| Third (S3) | Vibration as blood rushes into the ventricles during rapid filling (not a valve) | Early diastole; can be normal in children and young adults |
| Fourth (S4) | Atria contracting hard against a stiff ventricle | Just before S1; usually a sign of disease |
The interval from lub to dub is the ventricular systole (0.3 s); from dub to the next lub is 0.5 s. A murmur is an extra whooshing sound from turbulent flow, for example when blood leaks back through an incompetent (leaky) valve or squeezes through a narrowed one. A doctor listens with a stethoscope.
Stroke volume and cardiac output
- NCERT Stroke volume (SV): the volume of blood pumped out by each ventricle during a cardiac cycle, about 70 mL.
- NCERT Cardiac output (CO): the volume of blood pumped out by each ventricle per minute. CO = SV × heart rate = 70 mL × 72 = 5040 mL, about 5 L per minute.
- Athletes have a much higher cardiac output during exercise (it can rise five-fold), mainly by increasing stroke volume.
- Cardiac index = cardiac output / body surface area = 5 L/min ÷ 1.7 m2 ≈ 3 L/min/m2. It lets doctors compare people of different sizes.
- Frank-Starling law: the more the ventricles are filled (and stretched) at the end of diastole, the more forcefully they contract, so stroke volume rises with venous return.
The electrocardiogram (ECG)
NCERT An ECG is a graphical representation of the electrical activity of the heart during a cardiac cycle. A patient is connected to the machine with three electrical leads (one to each wrist and to the left ankle) for a standard record; a 12-lead ECG gives more detail.
Swipe the table sideways to see every column.
| ECG part | Represents | Typical duration |
|---|---|---|
| P wave | Atrial depolarisation, leading to atrial contraction | About 0.08 to 0.1 s |
| PQ (PR) interval | Time for the impulse to pass from SA node through the AV node | 0.12 to 0.20 s (about 0.16 s) |
| QRS complex | Ventricular depolarisation; starts ventricular contraction | About 0.08 to 0.1 s |
| ST segment | Ventricles fully depolarised; contracting | Normally flat |
| T wave | Ventricular repolarisation; the end of the T wave marks the end of systole | About 0.16 s |
| QT interval | Whole ventricular systole | About 0.35 to 0.42 s (shorter at fast heart rates) |
Counting the QRS complexes in a set time gives the heart rate. Atrial repolarisation does not show as a separate wave: it is tiny and happens at the same time as the QRS complex.
Swipe the table sideways to see every column.
| ECG change | Likely meaning |
|---|---|
| No P waves | SA node not firing; another part of the heart sets a slower rhythm |
| PR interval longer than 0.2 s | Delay at the AV node (first-degree heart block), e.g. in rheumatic fever |
| P waves not followed by QRS; atria and ventricles beat independently | Complete (third-degree) heart block |
| ST elevation, deep Q waves | Myocardial infarction (heart attack) |
| ST depression, flat or inverted T | Myocardial ischaemia (not enough oxygen to heart muscle) |
In complete heart block no impulses reach the ventricles, which then beat at their own slow ‘escape’ rhythm of about 20 to 40 per minute. Sudden pauses can make the person faint: these episodes are called Stokes-Adams attacks. The treatment is an artificial pacemaker: a small battery-powered device implanted under the skin below the collarbone, with a lead (electrode) passed through a vein into the right ventricle (and often the right atrium) to deliver regular impulses.
Regulation of heart rate
NCERT Normal activities of the heart are regulated intrinsically (auto-regulated by specialised muscles: nodal tissue), hence the heart is called myogenic. A special neural centre in the medulla oblongata can moderate the cardiac function through the autonomic nervous system.
Swipe the table sideways to see every column.
| Pathway | Neurotransmitter | Effect |
|---|---|---|
| Sympathetic nerves (cardio-accelerator centre) | Noradrenaline (norepinephrine) | Increase rate and strength of contraction, so cardiac output rises |
| Parasympathetic: vagus nerve (cardio-inhibitor centre) | Acetylcholine | Decrease rate and speed of conduction, so cardiac output falls |
| Adrenal medullary hormones | Adrenaline (epinephrine) | Increase heart rate and cardiac output |
- Vagal tone: on its own, the SA node would fire about 100 times per minute. The vagus nerve releases acetylcholine all the time, which brings the resting rate down to about 72.
- Baroreceptors in the walls of the aortic arch and carotid sinus detect stretch. When blood pressure rises they fire more, the cardio-inhibitor centre is stimulated, vagal output rises and sympathetic output falls, so heart rate falls. Marey’s law: heart rate is inversely related to arterial blood pressure (when other factors stay the same).
- Chemoreceptors in the aorta, carotid bodies and medulla detect a rise in CO2 (fall in pH) during exercise, and the medulla raises heart rate.
- Thyroxine raises heart rate indirectly by raising metabolic rate and the tissues’ oxygen demand.
- Ions: excess K+ slows the heart and weakens contraction; Ca2+ strengthens contraction, and a very high level can stop the heart in contraction.
- Age, sex and temperature: a newborn’s heart beats about 120 to 140 times per minute, an adult’s about 72; women have a slightly higher resting rate than men; heart rate rises with body temperature (fever).
HL Control of heart rate by the brainstem (C3.1)
- Receptors (baroreceptors and chemoreceptors) send impulses to the cardiovascular centre in the medulla.
- The medulla sends impulses along sympathetic nerves to speed up the SA node, or along the vagus nerve to slow it down.
- Adrenaline from the adrenal glands reaches the SA node in the blood and speeds it up, for example in the ‘fight or flight’ response.
- The heart does not need nerves to beat; nerves and hormones only change the rate set by the SA node.
6 Double circulation and coronary circulation
Syllabus link: NCERT XI 15.5 Circulatory Pathways, 15.6 Double Circulation; IB B3.2.13 HL (single circulation of bony fish versus double circulation of mammals)
Double circulation is the key design feature of heart and circulation in mammals and birds. Comparing vertebrate hearts shows how it evolved.
How the vertebrate heart evolved
NCERT All vertebrates have a muscular chambered heart. Fishes have a 2-chambered heart with an atrium and a ventricle. Amphibians and reptiles (except crocodiles) have a 3-chambered heart with two atria and a single ventricle, whereas crocodiles, birds and mammals have a 4-chambered heart with two atria and two ventricles.
Swipe the table sideways to see every column.
| Group | Chambers | Circulation | Key details |
|---|---|---|---|
| Fishes | 2 main (atrium, ventricle) + accessory sinus venosus and conus (bulbus) arteriosus | Single | Only deoxygenated blood passes through the heart (a venous heart). Path: sinus venosus → atrium → ventricle → conus arteriosus → ventral aorta → gills (oxygenated) → dorsal aorta → body → back to sinus venosus |
| Amphibians | 3 (2 atria, 1 ventricle) + sinus venosus and truncus arteriosus (pylangium and synangium) | Incomplete double | Right atrium gets deoxygenated blood (via sinus venosus), left atrium gets oxygenated blood from lungs; they mix in the single ventricle (arterio-venous heart). A spiral valve in the pylangium partly separates the streams into pulmocutaneous (lungs and skin), systemic and carotid (head) arches |
| Reptiles (most) | 3; ventricle partly divided | Incomplete double | Less mixing than in amphibians; separate pulmonary arch and two systemic arches |
| Crocodiles | 4 (complete ventricular septum) | Double | Left and right systemic arches are joined by the foramen of Panizza, so blood can bypass the lungs when diving |
| Birds | 4 | Complete double | Only the right systemic arch (aorta) remains |
| Mammals | 4 | Complete double | Only the left systemic arch remains as the aorta; the sinus venosus is merged into the right atrium as the SA node region |
Amphibians cope with mixed blood because they are cold-blooded (low metabolic rate) and their blood picks up extra oxygen through the skin (cutaneous respiration). Birds and mammals are warm-blooded with a high basal metabolic rate, so their cells need a large, steady oxygen supply: complete separation of oxygenated and deoxygenated blood in a 4-chambered heart makes that possible.
Double circulation in humans
NCERT Blood passes through the heart twice in one complete circuit, so humans have double circulation:
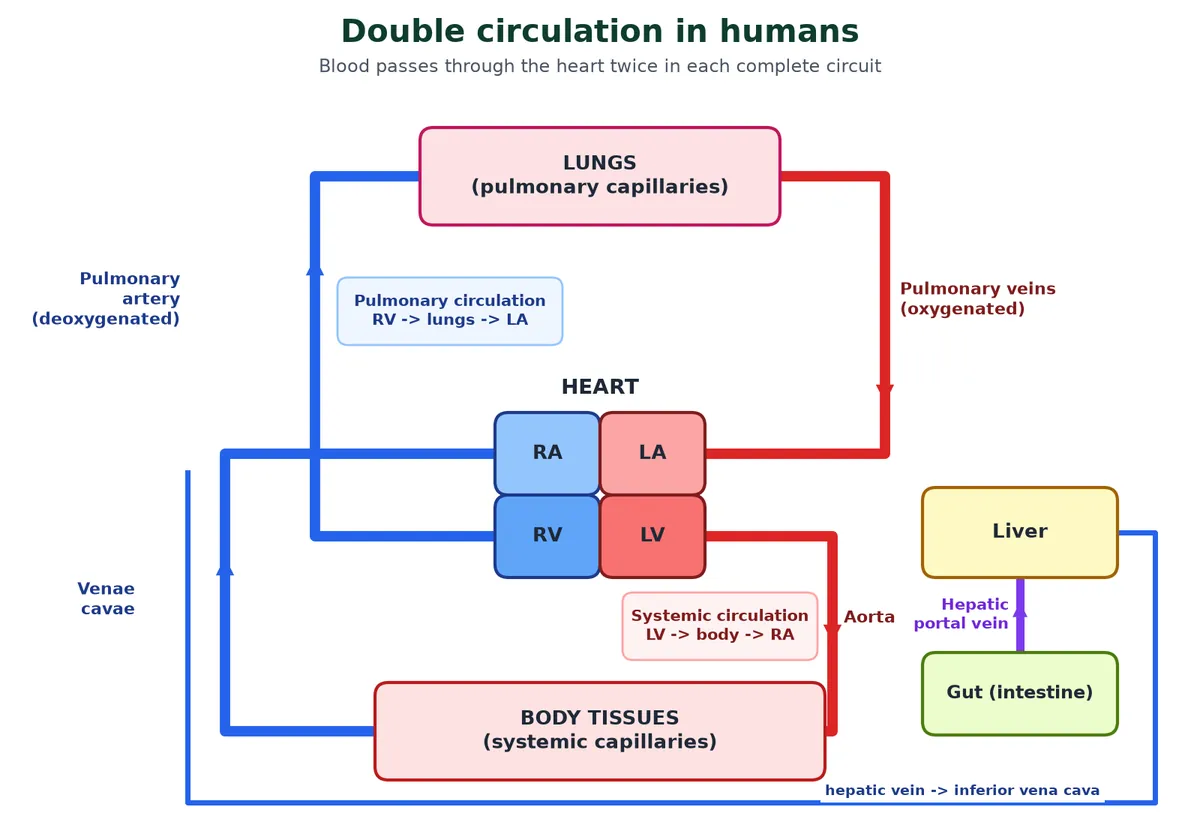
- Pulmonary circulation: right ventricle → pulmonary artery → lungs (oxygenated) → pulmonary veins → left atrium.
- Systemic circulation: left ventricle → aorta → arteries, arterioles, capillaries of the tissues (deoxygenated) → venules, veins → venae cavae → right atrium.
- The systemic circulation supplies nutrients, O2 and other essential substances to the tissues and takes CO2 and other harmful substances away for elimination.
HL Single versus double circulation (B3.2.13)
Swipe the table sideways to see every column.
| Feature | Bony fish (single) | Mammal (double) |
|---|---|---|
| Times blood passes through the heart per circuit | Once | Twice |
| Chambers | 1 atrium, 1 ventricle | 2 atria, 2 ventricles |
| Pressure in blood going to body | Low: pressure is lost in the gill capillaries | High: blood returns to the heart after the lungs and is pumped again |
| Where blood is oxygenated | Gills | Lungs |
Advantage of double circulation: the lungs get blood at lower pressure (protecting the delicate alveolar capillaries), while the body gets it at high pressure, so it reaches all tissues quickly.
Portal systems
Normally blood passes through one capillary bed between an artery and a vein. In a portal system, a vein carries blood from the capillaries of one organ to the capillaries of a second organ before it returns to the heart: a portal vein has capillaries at both ends.
- NCERT Hepatic portal system (all vertebrates): the hepatic portal vein carries blood from the intestine (and stomach, pancreas and spleen) to the liver before it is delivered to the systemic circulation. The liver stores glucose as glycogen, deals with excess amino acids (making urea) and breaks down old red cell products. The hepatic vein then carries blood to the inferior vena cava.
- Hypophyseal portal system: blood from capillaries in the hypothalamus goes to the anterior pituitary, carrying releasing and inhibiting hormones.
- Renal portal system: blood from the hind limbs passes through the kidneys first. It is well developed in fishes and amphibians, reduced in reptiles and birds, and absent in mammals.
Coronary circulation
NCERT A special coronary system of blood vessels is present in our body exclusively for the circulation of blood to and from the cardiac musculature. The heart cannot use the blood inside its chambers; its thick walls need their own supply.
- The right and left coronary arteries are the first branches of the ascending aorta, just above the aortic semilunar valve. They run over the surface of the heart and branch into the myocardium.
- Coronary arteries fill mainly during diastole, because contracting muscle squeezes them shut in systole.
- Deoxygenated blood is collected by cardiac veins into the coronary sinus, which opens into the right atrium (guarded by the Thebesian valve).
- A blockage of a coronary artery cuts off part of the heart muscle from oxygen: the basis of angina and heart attacks (section 7).
7 Blood pressure and cardiovascular disorders
Syllabus link: NCERT XI 15.8 Disorders of Circulatory System; IB B3.2.4 (pulse), B3.2.6 (causes and consequences of occlusion of the coronary arteries)
Blood pressure is the force that drives blood round the heart and circulation system, and most disorders of the heart and circulation involve abnormal blood pressure or blocked arteries.
What is blood pressure?
Blood pressure is the force blood exerts on the walls of the arteries. It is measured with a sphygmomanometer and written as two numbers in mm Hg:
- NCERT Normal blood pressure is 120/80 mm Hg. 120 is the systolic (pumping) pressure, during ventricular systole; 80 is the diastolic (resting) pressure.
- Pulse pressure = systolic − diastolic = 120 − 80 = 40 mm Hg.
- Mean arterial pressure (MAP) = diastolic + 1/3 (pulse pressure) = 80 + 40/3 ≈ 93 mm Hg. It is closer to the diastolic value because the heart spends longer in diastole.
How the reading is taken: the cuff is pumped up until it stops blood flow in the arm artery, then slowly let down while a stethoscope listens below the cuff. The first tapping sound (a Korotkoff sound, from blood spurting through the partly squeezed artery) marks the systolic pressure; the point where the sounds disappear marks the diastolic pressure. These are not the lub and dub of the heart valves.
Click to check: a reading is 140/95. What is the pulse pressure?
140 − 95 = 45 mm Hg. The reading is also in the hypertension range by the NCERT definition.
Disorders of the circulatory system
Swipe the table sideways to see every column.
| Disorder | What it is | Notes |
|---|---|---|
| Hypertension (high blood pressure) | NCERT Blood pressure higher than normal (120/80); repeated readings of 140/90 or higher | Leads to heart diseases and affects vital organs like brain (stroke) and kidney (nephron damage). Many guidelines now treat 130/80 as the start of high blood pressure |
| Coronary artery disease (CAD), atherosclerosis | Deposits of calcium, fat, cholesterol and fibrous tissue (plaques) in the inner lining (tunica intima) of coronary arteries narrow the lumen | Less blood and oxygen reach the heart muscle (ischaemia) |
| Angina pectoris | Acute chest pain when not enough oxygen reaches the heart muscle | Pain may spread to the left arm, neck or jaw; common in middle-aged and elderly people |
| Heart attack (myocardial infarction) | Heart muscle is suddenly damaged by an inadequate blood supply, usually a clot (thrombus) blocking a narrowed coronary artery | Dead cardiac muscle cannot regenerate; it is replaced by scar tissue |
| Cardiac arrest | The heart stops beating | Different from a heart attack; needs CPR and defibrillation |
| Heart failure | The heart is not pumping blood effectively enough to meet the needs of the body | Sometimes called congestive heart failure because congestion of the lungs is a main symptom |
HL Occlusion of the coronary arteries (B3.2.6)
- Causes: atherosclerosis narrows the artery; a plaque can rupture and trigger a clot (coronary thrombosis) that blocks it completely.
- Consequences: the heart muscle beyond the block is starved of oxygen; it cannot respire aerobically, cells die, and the heart may beat irregularly or stop.
- Risk factors: high blood cholesterol (high LDL), smoking, high blood pressure, diabetes, obesity, lack of exercise, family history (genes), age, and being male (women’s risk rises after menopause).
- Correlation is not causation: IB asks you to evaluate epidemiological data. A correlation between, say, saturated fat intake and CHD does not prove one causes the other; other factors may differ between the groups.
Treatment of blocked arteries
- Clot busters (thrombolytics) such as streptokinase and tissue plasminogen activator (tPA) dissolve a fresh clot.
- Angioplasty: a balloon on a catheter opens the artery, and a mesh tube (stent) keeps it open.
- Coronary artery bypass grafting (CABG): a vein from the leg or an artery from the chest is used to route blood around the blockage.
- Daily low-dose aspirin, statins (lower cholesterol) and lifestyle changes reduce the risk of another event.
Other heart problems in MCQs
- Rheumatic heart disease: after a throat infection with Streptococcus pyogenes, antibodies made against the bacterium’s cell wall (M) protein also attack similar proteins in the heart (molecular mimicry), especially the mitral valve. The scarred valve may leak or narrow, and the heart has to work harder.
- Arrhythmias: abnormal heart rhythms. A fast rhythm is a tachyarrhythmia; a slow one is a bradyarrhythmia, for example from SA node failure or AV block, and may need a pacemaker.
- Heart murmurs: abnormal sounds from leaky (incompetent) or narrowed valves.
8 Lymph and its functions
Syllabus link: NCERT XI 15.4 Lymph (Tissue Fluid); IB B3.2.10 to B3.2.12 HL (formation of tissue fluid, exchange with cells, drainage into lymph ducts)
Not all the fluid that leaves the blood comes straight back. The lymphatic system is the drainage network that completes the heart and circulation story.
From plasma to tissue fluid to lymph
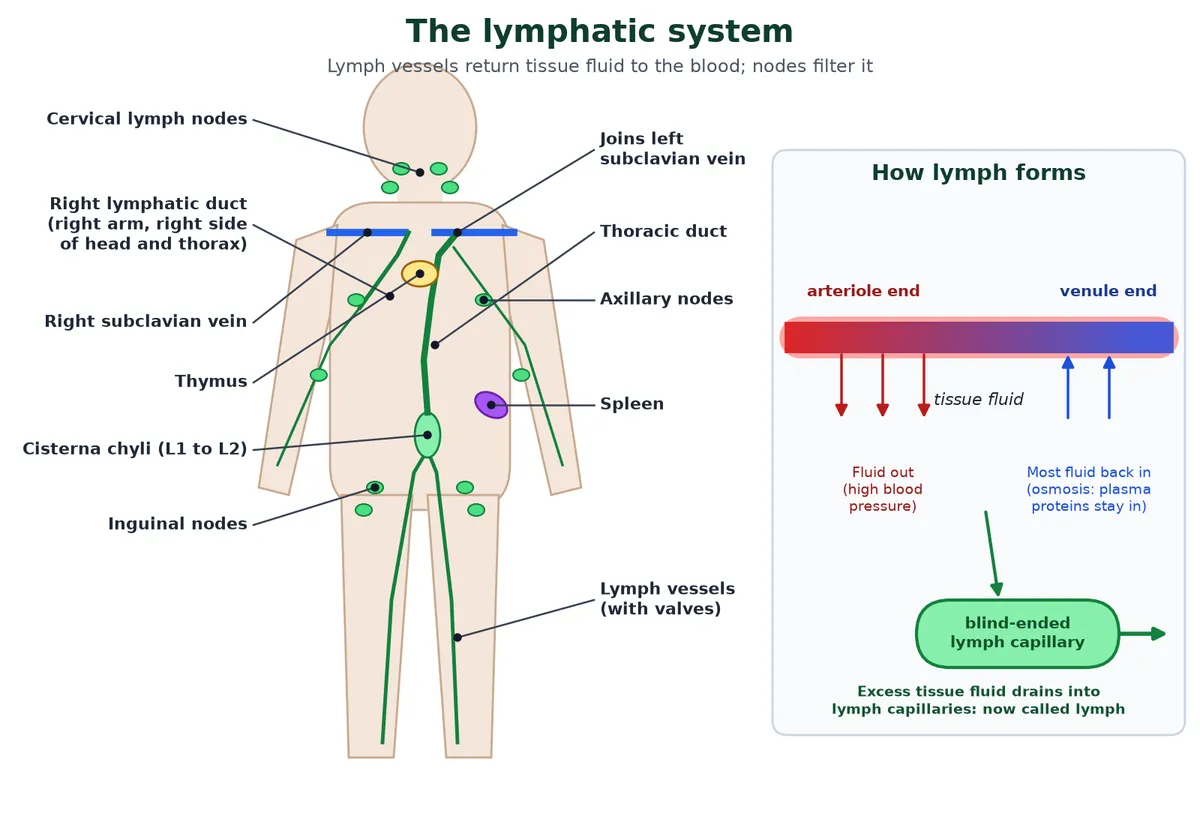
NCERT As blood passes through the capillaries in tissues, some water along with many small water-soluble substances move out into the spaces between the cells of tissues, leaving the larger proteins and most of the formed elements in the blood vessels. This fluid released out is called the interstitial fluid or tissue fluid. It has the same mineral distribution as that in plasma. Exchange of nutrients, gases, etc., between the blood and the cells always occurs through this fluid.
HL Tissue fluid formation and drainage (B3.2.10 to B3.2.12)
- Pressure filtration: at the arteriole end of a capillary, blood pressure is higher than the osmotic pull of plasma proteins, so water and small solutes (glucose, oxygen, ions) are forced out through gaps in the capillary wall. Large proteins and cells stay in.
- Exchange with cells: cells take what they need from the tissue fluid by diffusion and active transport and release CO2 and wastes into it.
- Reabsorption: at the venule end, blood pressure has fallen, and the plasma proteins draw water back into the capillary by osmosis.
- Drainage: less fluid returns than left (roughly 10% is left over). This excess enters blind-ended lymph capillaries, whose walls have flap-like gaps that let fluid in but not out. Lymph vessels have valves, and lymph is moved by squeezing of nearby muscles, then returned to the blood in the subclavian veins.
The lymphatic system
NCERT An elaborate network of vessels called the lymphatic system collects this fluid and drains it back to the major veins. The fluid present in the lymphatic system is called the lymph.
- Lymph capillaries join into lymph vessels, which pass through lymph nodes (filters full of lymphocytes and macrophages) and join two main ducts.
- The thoracic duct, the largest, begins in the abdomen at a sac called the cisterna chyli (at the level of the first and second lumbar vertebrae). It drains lymph from both legs, the abdomen, the left side of the chest, the left arm and the left side of the head, and empties into the left subclavian vein (where it meets the left internal jugular vein).
- The right lymphatic duct drains the right arm and the right side of the head, neck and chest, and empties into the right subclavian vein.
- Lymph flows only one way: from the tissues towards the heart. There is no pump; valves and muscle movements keep it moving.
- NCERT Fats are absorbed through lymph in the lacteals present in the intestinal villi. Lymph that is milky with absorbed fat is called chyle.
- Lymphoid organs: lymph nodes, spleen, thymus, tonsils and Peyer’s patches.
Functions of lymph
- Returns tissue fluid and leaked plasma proteins to the blood, keeping blood volume steady. Without it, fluid would collect in the tissues (oedema).
- NCERT Lymph is a colourless fluid containing specialised lymphocytes which are responsible for the immune responses of the body.
- Lymph nodes filter out bacteria and debris; lymphocytes there make antibodies.
- NCERT Lymph is an important carrier for nutrients, hormones, etc.
- Carries absorbed fats (as chylomicrons) from the intestine to the blood.
Swipe the table sideways to see every column.
| Feature | Blood plasma | Tissue fluid | Lymph |
|---|---|---|---|
| Where | Inside blood vessels | Around cells | Inside lymph vessels |
| Proteins | High (albumin, globulin, fibrinogen) | Low | Low (some leaked proteins) |
| Cells | RBCs, WBCs, platelets | Few WBCs | Mainly lymphocytes; no RBCs, no platelets |
| Oxygen and nutrients | High | Medium | Low |
| CO2 and wastes | Lower | Higher | Higher |
| Clotting | Clots (has fibrinogen) | No | Clots slowly |
If lymph vessels are blocked, fluid collects and the tissue swells. In filariasis, Wuchereria worms live in the lymph vessels of the legs and cause a huge swelling called elephantiasis.
9 Key terms
Learn these key terms for blood, the heart and circulation; most one-mark questions test a definition.
Swipe the table sideways to see every column.
| Term | Meaning |
|---|---|
| Plasma | Fluid part of blood: 90 to 92% water, 6 to 8% proteins. |
| Serum | Plasma without clotting factors. |
| Haemoglobin | Iron-containing red pigment in RBCs that carries oxygen. |
| Agglutination | Clumping of red cells when antigens meet matching antibodies. |
| Erythroblastosis foetalis | Destruction of foetal RBCs by an Rh− mother’s anti-Rh antibodies. |
| Thrombin | Enzyme that converts fibrinogen into fibrin. |
| Myogenic | Heartbeat starts in the heart muscle itself. |
| SA node | Pacemaker of the heart, in the right atrium. |
| Cardiac cycle | One complete systole and diastole of atria and ventricles (0.8 s). |
| Stroke volume | Blood pumped by each ventricle per beat (about 70 mL). |
| Cardiac output | Blood pumped by each ventricle per minute (about 5 L). |
| Double circulation | Blood passes through the heart twice in one circuit. |
| Portal vein | Vein with capillaries at both ends (e.g. hepatic portal vein). |
| Blood pressure | Force of blood on artery walls; normally 120/80 mm Hg. |
| Atherosclerosis | Plaque build-up that narrows arteries. |
| Tissue fluid | Fluid that leaks from capillaries and bathes cells. |
| Lymph | Tissue fluid inside lymph vessels; carries lymphocytes and fats. |
10 Common doubts about blood, heart and circulation
These are the questions students keep asking on Reddit, Quora, Stack Exchange and NEET doubt pages. Each answer is ours; the link shows where the doubt comes from.
O negative is the universal donor, but its plasma has anti-A and anti-B. Why doesn’t that attack the patient’s cells?
Because what is usually transfused is packed red cells, with most of the plasma removed. The rule ‘O is the universal donor’ is about red cell antigens: O− cells carry no A, B or Rh antigen, so the patient’s antibodies have nothing to attack. The small amount of donor antibody left is diluted in the patient’s blood. For plasma the rule is reversed: AB plasma (no antibodies) is the universal plasma. (Doubt seen on reddit.com)
If the pulmonary artery carries deoxygenated blood, why is it called an artery?
Arteries and veins are named by direction, not by the oxygen they carry. An artery carries blood away from the heart; a vein carries it towards the heart. The pulmonary artery takes blood from the right ventricle to the lungs, so it is an artery even though its blood is deoxygenated. The pulmonary veins are the matching exception. (Doubt seen on biology.stackexchange.com)
Why is the left ventricle wall so much thicker than the right?
Both ventricles pump the same volume per beat. The left ventricle has to push blood through the whole body against high resistance (about 120 mm Hg), while the right only pushes it through the nearby lungs (about 25 mm Hg). More muscle means more force. A thick right ventricle would actually damage the delicate lung capillaries. (Doubt seen on quora.com)
Why is the first Rh-positive baby of an Rh-negative mother usually safe?
The mother has no anti-Rh antibodies to begin with; she makes them only after being exposed to Rh+ blood. During the first pregnancy the placenta keeps the two bloods apart. The main exposure happens at delivery, when the first baby is already born. Her antibodies then threaten the next Rh+ baby, which is why anti-Rh antibodies are given to her right after the first delivery. (Doubt seen on medicneet.com)
Why is there no wave for atrial repolarisation in the ECG?
The textbook answer is that it is hidden by the QRS complex, which happens at the same time. The fuller answer is that atrial muscle is thin, so the repolarisation signal (the Ta wave) is very small and spread out; even when there is no QRS, as in some heart blocks, it is hard to see. For exams, ‘masked by the QRS complex’ is accepted. (Doubt seen on reddit.com)
Capillaries are the narrowest vessels. Why isn’t resistance highest there, and why is blood slowest there?
One capillary has a high resistance, but billions of them lie side by side (in parallel), so their combined resistance is lower than that of the arterioles, which are the main site of resistance and pressure drop. Speed depends on total cross-sectional area: the capillary bed is about 1000 times wider than the aorta, so blood moves slowest there, which gives time for exchange. (Doubt seen on biology.stackexchange.com)
Why does the AV node delay the impulse?
If the ventricles contracted at the same moment as the atria, the atria would not have finished emptying, and the ventricles would push blood back up. The AV node cells are small, have few gap junctions and conduct slowly, giving a delay of about 0.1 s. The PR interval on an ECG measures this delay. (Doubt seen on reddit.com)
If blood has clotting factors, why doesn’t it clot inside our vessels?
The factors circulate in an inactive form, and clotting needs a trigger: damaged tissue or exposed collagen under the vessel lining. Healthy endothelium is smooth and releases substances that stop platelets sticking, and natural anticoagulants such as heparin and antithrombin keep the cascade switched off. When a vessel lining is damaged, as in atherosclerosis, a clot can form inside it: a thrombosis. (Doubt seen on reddit.com)
Are tissue fluid and lymph the same thing?
Almost. They are the same fluid in different places. Tissue fluid is the fluid around cells; once it enters a lymph capillary it is called lymph. Lymph collects more lymphocytes as it passes through lymph nodes, and lymph from the intestine also carries fat. Both have much less protein than plasma. (Doubt seen on medicneet.com)
11 FAQ
Short answers to the questions we are asked most about the heart and circulation.
What is covered in the heart and circulation chapter for NEET?
NCERT Class XI Chapter 15, Body Fluids and Circulation: blood and its formed elements, blood groups, coagulation, lymph, the human heart, cardiac cycle, ECG, double circulation, regulation of heart activity and circulatory disorders.
How long is one cardiac cycle?
About 0.8 s at a heart rate of 72 per minute: 0.1 s atrial systole, 0.3 s ventricular systole and 0.4 s joint diastole.
What causes the lub and dub sounds?
Lub is the closure of the AV (tricuspid and bicuspid) valves at the start of ventricular systole. Dub is the closure of the semilunar valves at the start of ventricular diastole.
Which blood group is the universal donor?
O negative for red cells, because the cells carry no A, B or Rh antigen. AB positive is the universal recipient.
What is the difference between a heart attack and cardiac arrest?
In a heart attack, part of the heart muscle dies because its blood supply is blocked. In cardiac arrest, the heart stops beating. A heart attack can lead to cardiac arrest.
Why is the human heart called myogenic?
Because each beat starts in specialised heart muscle, the SA node, not in a nerve. Nerves only speed it up or slow it down.
Which IB topics does this page cover?
IB Biology B3.2 Transport (blood vessels, heart, cardiac cycle, tissue fluid and lymph, with HL parts marked), C3.2 blood clotting and C3.1 control of heart rate.
12 Quick check
Tap each question to reveal the answer and check your grasp of blood, the heart and circulation before trying the full question set.
Test yourself on the heart and circulation
1. What percentage of plasma is water?
90 to 92%.
2. Which plasma protein maintains osmotic balance?
Albumin.
3. Name the graveyard of RBCs.
The spleen.
4. A person has anti-A antibodies only. What is their blood group?
B.
5. Which enzyme converts fibrinogen to fibrin?
Thrombin.
6. Which valve lies between the left atrium and left ventricle?
The bicuspid (mitral) valve.
7. Where is the pacemaker of the heart?
The SA node, in the upper right corner of the right atrium.
8. Give the duration of ventricular systole.
0.3 s.
9. What does the T wave of an ECG show?
Ventricular repolarisation.
10. Calculate cardiac output if stroke volume is 80 mL and heart rate is 75 per minute.
80 × 75 = 6000 mL = 6 L per minute.
11. In which animals is only the right systemic arch present?
Birds.
12. Into which vein does the thoracic duct open?
The left subclavian vein.
More practice
Ready for exam-style questions? Try our body fluids and circulation MCQ set for NEET, then download the IB and NEET question set below.
Ready to practise? Download the Blood, Heart and Circulation IB and NEET question set with markscheme (25 MCQs + 6 structured questions, 65 marks, free for signed-up members).
⬇ Download practice questions (PDF)© competitorspoint.com · Biology notes. All diagrams are original to competitorspoint.com.